



























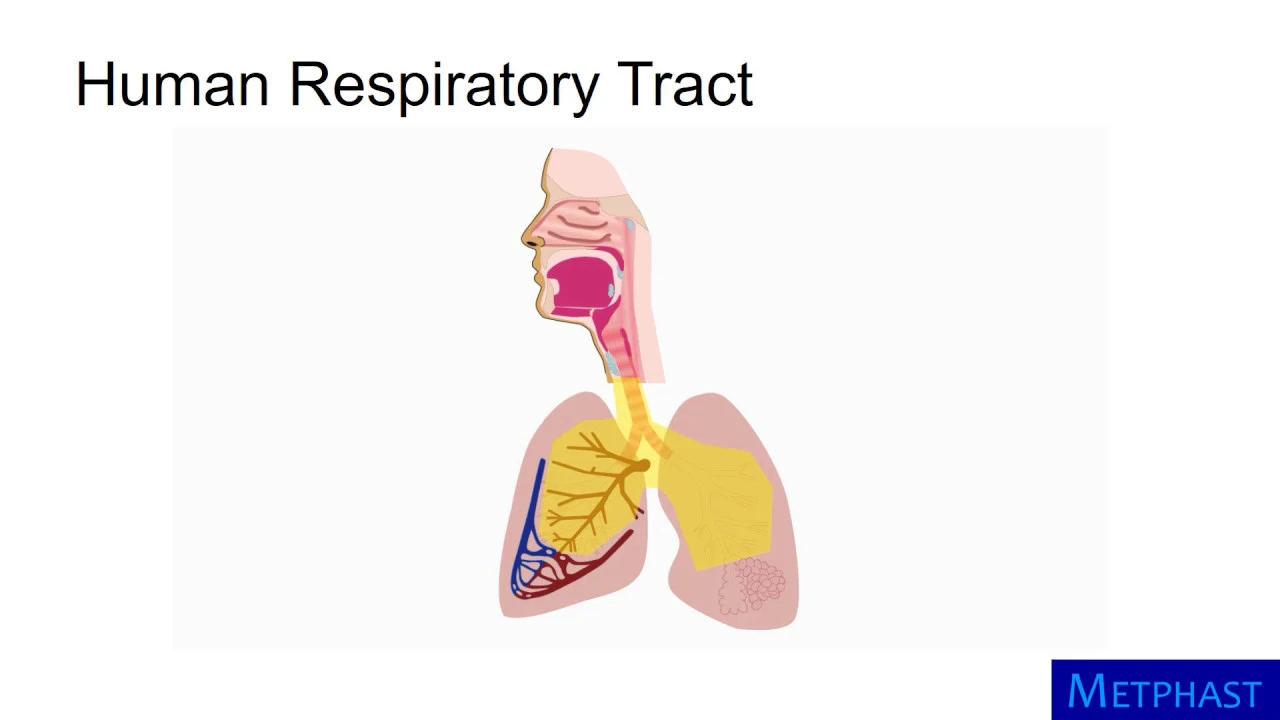
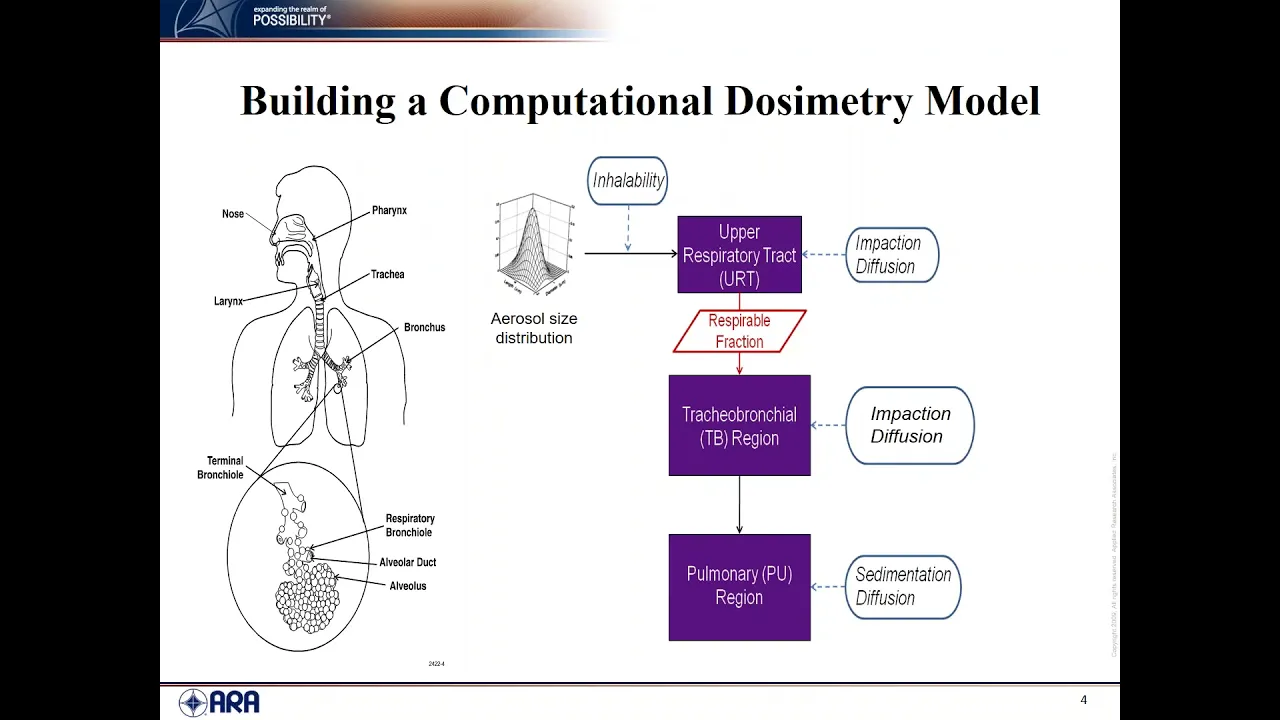


Human lung tissue models, including the Normal Human Bronchial Epithelial (NHBE) model and microengineered lung-on-a-chip devices, provide physiologically relevant alternatives to animal testing for inhalation toxicity assessment. The NHBE model uses primary human bronchial epithelial cells that differentiate into seven cell types (ciliated, goblet, Clara, intermediate, and basal cells) forming a stratified structure with tight junctions, enabling real-time monitoring of barrier integrity through electrical resistance measurements and detection of inflammatory responses via cytokine profiling. The lung-on-a-chip technology further advances this field by creating microfluidic devices that mimic the alveolar-capillary interface with cyclic breathing motions, allowing researchers to model complex physiological processes such as immune cell recruitment during infection and drug-induced pulmonary edema. These human tissue-based models offer improved predictability for respiratory toxicity compared to traditional animal models, with validation studies showing 77% correlation with in vivo results, and represent a promising approach for reducing reliance on animal testing while advancing understanding of respiratory disease mechanisms and developing safer therapeutic interventions.
Alternative Approaches for Acute Inhalation Toxicity Testing | PSCI Webinar
Added:the broadcast is now starting all attendees are in listen only mode welcome everyone to the sixth and final webinar in our series on alternative approaches for acute inhalation toxicity testing my name is Amy clippinger I'm the associate director of the P international science Consortium and I will be co-moderating to webinar with Dr David Allen who works as a contractor supporting the US MTP inter agency center for the evaluation of alternative toxology methods also known as nedum I'd like to thank you all for joining today's webinar and before I introduce our speakers I'll run quickly through a few Logistics the slides and recording of today's webinar will be posted online at the first link on your screen within a few days the previous five webinar recordings are posted there as well everyone is muted now if you have a technical question for me anytime during the presentation you can use the question box which is located in the go-to webinar panel on the right hand side of your screen we'll hold all questions for the speakers until the end of both presentations if you have a question for one of our speakers you can type it in that same goto webinar question box and Dave will ask your questions to our speakers during the Q&A period at the end but please feel free to send in your questions anytime during the webinar the earlier the better so our first Speaker today is Dr Kelly baru Kelly is the director of the lung and particle research group at the school of biosciences at ciff University in the UK she has a background in electron microscopy and lung toxicology and has built an international reputation in the field of air pollution and human health and holds numerous appointments in the US and UK on funding bodies advisory councils professional societies and journal editorial boards that focus on environmental health her research focuses on the determination of intelligent biomarkers of exposure and harm in the respiratory system with a particular interest in understanding how pollutant compromised lung biochemistry and alter gene expression and protein expression to drive disease mechanism Kelly well thank you for that introduction Amy and I'd like to begin by thanking yourself and P International for giving myself and my colleague um Zoe pric the chance to um showcase our lung models today so I'm going to be telling you about the normal human bronchial epithelial model and the metabolon model and we use these for inhalation toxicology applications but they're very versatile and they rely on using human primary tissues okay so the reason for our research and why we built these models is because the burden of lung disease so myself and Zoe are respiratory toxicologists so I want to set the scene behind our models for example globally uh mortality for respiratory diseases ranks number two on the mortality list and in the United Kingdom in Western Europe it's number one and indeed in the United Kingdom one in four people die from a respiratory disease and the FDA has said recently that there's been no innovation in the last 25 years and they believe to the fact that we're working with animals and that we need to move to human tissues so that we can get some basically useful results some human data generate from human human endpoint data and another problem too is that air pollution has an um time before they die so you can actually lose up to five years of your life depending on where you live die early that is um the wh says in the next 10 years we're going to have um 30% increase again in um crds that's chronic respiratory diseases and then finally by 2020 which isn't that long about 12 million I and course with a lot of people like s believe that the reason why we have no Innovations and we're stuck with this problem is because of traditional animal testing and the course if you're familiar in this field um with inhalation we use a lot of Road models so we use hamsters and mice and guinea pigs Etc but the problem is that their physiology and Anatomy is so different from ODS that you really cannot get good extrapolation um typically before the Advent of human tissues we would take the rodents and then we would instill particles into them say air pollution and they'd either to be um fed nose only or whole body exposure so inhalation or insallation with then we would just leave them there for acute or chronic times then we would euthanize them we would rinse out their lungs look for any type of um inflammatory mediators then we would look at the histology and then we would try to come to identifying some biomarkers to say if this happens into in the rat this is going to happen to man and it just doesn't work so this kind of led to the Advent of um human tissue Banks and then Beal models and this is where Zoe and I started off about 10 years ago we were able to startop buying tissu so we moved away from working with the animals and we started buying tissues and we started with lonza and we buy their um normal human bronal epithelial cells they isolate these now from um live donors or even postmortem donors up to three days postmortem so that's called medical waste tissues and what we do then is we get um these isolated for us we remove the basil epithelial cells so these are stem cells and then we divide the 3D formula we have a knoow document on that so you can buy a license to um to generate it yourself now this differentiates cells and the basil cells go right into um about seven different cell types so the seven cell types that you find in the bronch epithelium this is grown in the air liquid interface just how we breathe and you can get ciliated cells golet cells they secrete mucin Cav cells they secrete oxidants when you have an irritation in the lung intermediate cells and basil so the basil cells will return into the intermediates then the intermediates sit there and if you have um The claric Goblet or ciliated cell damaged which means you're causing a hole in that area the intermediate cell will turn into one of those and plug that hole so it's a very tiny little system it's only 5 millimeters in diameter and working with milor we've come up with a system that works quite well using a microporous membrane so you don't have to have um fibroblast sty AO collagen you can work right off this membrane and then from there after the experiment you can take the tissues and do histology you can do toxicogenomics proteomics take the apical wash and see if there's any proteins or inflammatory mediators you can look at the basil media through hlc and see if you have any um metabolism going on okay so that's the microng model right so why why are we using that model right now why are we going to all this trouble to characterize it well it's Pudo stratified like you finded in Vivo you get the seven different cell types but they can go layers up to five five to seven layers so if you're working with submerged cell culture then you'd um only get one type of cell a monolayer and you um yeah one cell type just a monolayer um the the other reason that we use these nhb cells is that you get tight junctions and adherent Junctions you also get desmon and hemid desmon Celia and microvi they secrete cyto kindes and mucin and they're non-cancerous or there's no transfected genes right so basically we created mucco phenotype just like you find um in the human situation in the lung so these are this is the membrane here these are um light microscope pictures tadine loose semi thin sections basil cells down here you have the garblet cell you can see the mucin in there you can see the long cyia they're about 10 microns in um length Micron in diameter just like you find in Vio ciliated cells um clar cells here and the intermediate cells and if you look at semm here you see a bit of irritation and the the gbet cells swen up so it's still a mucin and that mucin will then be released and the Celia be back and forth and they spread the muin across the whole surface there and it's like fly paper so you can trap debris that you inhale and then try to flush it out all right and the other interesting thing about um cell culture too is that um you get basil bodies and you get real cyia so what I mean by that is that when you do the transmission electron microscopy you'll have the axine the 9 plus2 organization there now when you work in the submerged couches you might get little stubby cyia they're really kind of like micro and they don't have this 9 plus2 Arrangement so we know we're getting true SOA here right for secretions well you can see the muin here the glyx and in Vivo there's the tips to um stick out and then you have all of the muin inside there to trap fly paper and that's exactly what's having happening in vro as well they beat synchronously and if they're in your body they beat up towards your mouth so that you would remove them through the system by spitting swalling or sneezing um in addition to with um submerged cultures you won't find this but you will also won't find your tight junctions or if they do they're weak we have lovely tight tight junctions adherence Junctions desaz zones and I don't have an image but we have he heavy desaz zones as well we see o1 in a clothing forming at days one and then by day 33 we see all of the tight junctions there now some of the smge couches don't even form the you know the tight junctions to this level so they're a bit leaky all right now the system you use is really simple um so three-step process after you grow these cells it take about two weeks to grow then you have um four weeks to grow and two weeks to use them you put your Compound on that's either going to be um it could be a liquid it could be nebulized powder live it onto the surface we keep it for the amount of time they you're interested in say acute right then you have to wash it off with PBS and then you can take that PBS wash and that can be G taken off and you can do all kinds of conventional talk sasses can take the tissues off and again the basil media and do everything that you can do right now with um not normal tissues right so and the important tool for us is called the um the endome chamber so we measure tier so here's the eone here's a chamber and what we're looking for is electrical current traveling through the apical and basil part of the cell and that tells us if we have a tight barrier if it's a tight barrier it's a healthy culture if there's a rupture in the barrier then we know there's been injury so you put your little um insert inside there and you do the measurement so high resistance High ohms 2,000 ohms you have a healthy barria at low resistance you'll have holes here that suggests that the tight junctions of rubed or cell cells have actually slued off the membrane and you know you've had some injury here so that's the principal tool that we use along with conventional toxicology right and here's some example data here this was three different donors show you that there's very little variability from day one to about day 15 we have this rapid growth and some people use their cultures from about day 18 onwards and we wouldn't recommend that because it takes day 21 to get the silia to grow the full length so we start using about day 24 and then we work all the way up to Day 36 so it gives you a nice window to do acute repeat or um chronic studies then by about Day 36 the culture demises so it's a twoe window all right so I'm going to show you some examples from Zoe's PhD so we looking at LPS here so um she's treated the couches LPS and the first thing you see happens is that the tear bottoms out so that means the tight junctions have um become leaky and the cell doesn't like the the LPS so it's an irtin and here is the ATP now that's some atps say cell viability you can see the cells having a bit of hesis there but then eventually they kind of keep up with it and they fall down so you always want the tier and ATB to be doing the same thing here obviously we're having a toxic reaction if you have a look at the hystology it doesn't look like much here in the upper layers the middle you see a little damage for gd50 here gd5 you having um spaces and um cyalis I think they call it Vues between the basal body but if you look at the semm the surface looks okay so that's why we recommend that you do semm temm and LM because right here if you look at the surface think it's fine but down here there's some damage there's obvious damage here at a toxic dose 20% with LPF throughout the whole system and then here you see the filiated cells actually slopping off and balling up suggesting a ptosis is some necrosis and here so you get the the same type of reactions that you see in Vivo and the initro situation with this model okay so now zo we did a little work on cyto kindes to see if we get any response so the red suggests that we have severe response and the blue is a mild response so this is for the the TD5 I'm going to show you a matrix in a minute so I just want to quickly show you this data then we did it for four hours that's the striped um red and blue and again severe and Mild with the colors but if you take all this information and put it in the Matrix we could learn a lot about what happened in those cell couches so at 24 hours for the gd5 we had a um we had a severe reaction nothing at 4 hours and then at 24 that that reaction is still persisting so that suggests that we have mediators of injury Happening Here with that cyto then you come down here TD5 we're having a low level of injury but by four hours and 24 hours it's persisting suggesting that you you're able to discern between um low and severe toxicity here if you come down to panel B okay we have severe toxicity here at cd20 for 4 hours persisting at 24 so that suggests severe injury and finally this is a nice one down here five nothing happening at 24 hours for TD5 and 20 this suggests here at the acute level that we're looking at early indicators of uh injury so that's a nice way to use cyto Kines as a biomarker in the system and this was an ala system as well for the cyto Kines it's inexpensive quick okay so we worked with Astro zenica they funded Zoe's PhD they asked her to look at about 25 compounds A1 to 25 so we were asked to determine if they were irritants or not we went into this blind we used ATP chair and Bradford and then we predicted av14 was not irritant z9 was a possible and 28 was irritant we then had to prove this with histology and we've did it here A1 14 no irritant it's beautiful the membrane five seven layers all cell types of vilia now we have mild injury which we predicted and now start seeing vacu and then the atin complete D differentiation of the whole system all we have left here are basil cells and that's it and most of the layers five layers of sloft off and then just to add bonus here I show you A1 they said that in Vivo that was not an irritant but when we did our work in histology we showed that was an irritant so in this this example here they did the animal study at the same time that we did the EnV study and we came out with 77% correlation which now suggests that they should be pre-screening with our system and maybe in the future not even have to go into animals I just do a final proof of concept so that was quite exciting correlation right the last thing we did and I can't tell you too much because we're still putting IP in place and and getting our patents so we haven't been able to publish is we've got this metabol along now so what we've done is we've taken donam match to pyes so we've taken liver cells from the people where we got the um epithelial cells from we grow the hepatocytes in the well um where you keep the food then we put the um so the heyes mature in about five seven days not less than that then we grow the nhbs on top they share a co-culture media which we designed and they can go for about 10 days what you can do is test whether the parent compound is toxic once it's been biotransformed and example here with hlc okay we looked at for we looked at detection of cetto Morphin um after 24 hours exposure to fastin so here we have nothing so Hep alone of course you're can to see biot transformation that's maybe a little with nhb so some inner inert um transformation and then when you put the two together co- culture we had the biot transformation and we got the correct product out another example and we went through the whole classic panels about 12 different um substrates you had to look work with liver to prove that you had biotransformation right so we looked at detection of dextrorphan um after incubation with dextrorphan hard to say these words sorry so again we saw the um transformation here of the liver uh a bit of inate on its own but when you put them together we definitely got some bio transformation and we got the product that we were expecting um so that's the metabol lung there that's all I can say about that right now and until we can do some publishing so in conclusions really as uh inhalation toxic you saw that the huge problem that we're facing right now and the Say by 2030 that um respiratory disease chronic respiratory disease would be the biggest killer on the planet by 2030 so we have some problems to deal with using animals we haven't been able to get understanding that we need so that we can come up with some clinical and therapeutic mitigations so now we're using these pathophysiological models the metabol and the um the microl lung and we're starting to get UL ances suggesting that you know we can move away and Zoe and I are interested in you know complete replacement um so human tissue based models we believe are the way to go um in terms of all the work we've done we've characterized the model to death we know the ratio in the human body of cated cells the garblet cells Etc all the secretions everything that's going on so we the model very well characterized and we feel that it can now step in and be a viable um alternative to using the road model you have a good window to do a cute t and repeat remember primary cell couches don't last that long so a twoe window is very good it's very cost effective one donut qu bile gives you 500,000 cells and we can get 350 of these um little micro lungs to work with and probably for less than 2,500 pounds and that includes all the consumables the media the bullet kits Etc all right in terms of the metabolon it opens new avenues for us we can start looking at multi-organ toxicity from just using a filter well bioreactor and these things are great you can buy them right off the shelf they're easy to use my husband's a geologist and he's able to do carry out this work you don't need specialist training and they allow affordable High through put um work which is nice and then finally I think you know even though we've built these for inhalation toxicology there's application for testing pesticides for testing perfumes we've done work for uni lever testing hairsprays um food products Etc so just doesn't have to be limited to working on air pollution and again our remit really is we're looking for complete replacement okay thank you um any questions I think I did that in 20 minutes hello so hi Kelly this is Dave Allen co- moderator of the webinar we do have a couple of questions but I think we're gonna hold those to the end of the webinar sure don't mind okay I'll go mute now okay I think Dr clippinger is having some telephone issues um but uh I'll go ahead and introduce Dr Hu we have our second speaker today is Dr Dan hu Dan is assist as an assistant professor and will Fam Family term and DOW chair in the department of biochemistry at the University of Pennsylvania he is a pioneer of organon a chip technology and his research group at 10 focuses on developing microengineered models of human anatomy and physiology for a wide variety of biomedical applications Dan has won many including the John J Ryan medal from the Royal College of Surgeons in Ireland design of the Year award from London design Museum NIH director's new innovator award analytical chemistry young innovator award the Ted he's been a tedex fellow uh best publication award and best postdoctoral award from Society of Toxicology and Fally that whis technology development Fellowship from Harvard and many others very pleased to have Dr HUD today to talk about microengineered physiological biomimic mimicry human organs on chips take it away do all right thank you thank you for the introduction and um I'd like to start uh by thanking the uh organizers for the opportunity to speak at this webinar so uh by way of quick introduction uh let me start by tell you a little bit about uh what kind of research we do in my laboratory so research in my lab uh basically revolves around uh developing these microfabricated devices uh that we use to grow human cells and also mimic the complex structure and environment uh of the of the of human organs in human body in ways that have not been possible using traditional cell culture models and techniques and uh the idea is to use these systems microengineered models of human organs uh to be more exact functional units of human organs for a variety of applications for drug testing toxicology screening environmental monitoring mechanistic disease studies and so on so we call these uh uh devices or systems uh human organs and a I'm sure you you've heard of it so what I like to do uh today is to introduce this technology to you to you guys and help you understand uh what's possible with this technology using uh a couple of human Organo chip models we're developing in my laboratory so i' like to start by telling you a little bit about uh microfluidic devices uh designed to mimic the human lungs I think these models are directly relevant to the theme of this webinar series okay so as you probably know uh the lung is a very complex organ consisting of a functional units called the Alvi so these are microscopic airx de in the lung that expand and contract uh you know during respiration and these aosc are covered with pulmonary capillaries to enable gas exchange and the interface between an alvus and surrounding capillaries is composed of a lung tissue alv Epal tissue on one side capillary tissue on the other side uh separated by this very very thin interstitial membrane so to mimic this interesting structure and also the dynamic environment of the Alvar system uh we used microfabrication techniques uh to build this device uh called human breathing Along on a chip so this photo shows the entire device uh the device is about the size of a computer memory stick and it's made of uh transparent and also biocompatible uh silicon elastomer called pdms polyline and if you look at the cross-section of the device um there are these two cell culture Chambers separated by the thin p flexible membrane so what we can do here is to culture lung cells on one side and capillary cells on the other side to mimic the original structure of the the AIL capillary interface and what we can also do is to apply cyclic vacuum suction to the side Chambers to stretch the tissue layers to mimic breathing motion cyclic breathing motions in this microfic device so this is a realtime uh movie of a membrane stretching uh in our microtic device and and the pores shown in this movie are are por uh pan anons joining this movie are pores on the membrane so this device uh basically allows us to culture human cells in a very physiological environment in this case air on the lung side and blood flow like liquid flow on the capillary side it eventually allows us to form this living bolar tissue that looks like the structural unit of the lung so I'm skipping a lot of details but we did the very thorough biochemical characterization morphological characterization to confirm that these tissue layers indeed resemble the original Al Capal interface but so this is interesting but what's more interesting is that the uh so this model looks like the the lung but also it functions like the lung so this model allows us to mimic uh not only tissue specific you know morphology differentiated morphology and functions but also more complex organ level functions integrated functions that arise from interactions between multiple tissue types so to demonstrate this idea i' like you to think about lung infection as an example so during a lung infection uh for example these bacterial cells in the lung in the alv ax stimulate alv epithelial cells and also Rin immune cells like macrophases to produce and secret pre-inflammatory saines that diffuse through the tissue layers and activate the uh the endothelial cells in the surrounding capillaries and as you'll know when this happens the the white blood cells like neutrophils are circulating in the blood patrolling the body actually they sense the the chemical gradient and also activation of endothelial cells so what they do is they stick and they squeeze themselves through the capillary tissue into the alv air sex and once inside the air sex they actually are Guided by uh the chemical gradient and they uh you know migrate actually crawl directly towards the side of infection and this is not quite how they crawl but uh uh for just a demonstration purposes and when they get there they try to resolve the infection uh by engulfing the Bia so this is how our long fights of infection and as far as I know this is one of the most complex integrated organ level functions that occur in the respiratory system so the important question here is can this long chip system do this so let's take a look so this movie shows a fluorescently taged primary human neutr fils flowing in the capillary channel of the lachip device so as you can see here nothing interesting happens but when we introduce bacterial cells on the long surface to mimic pulmon infection as you can see uh these wet blood cells actually stick to the capillary tissue because now the endal cells have been activated and so this is my favorite movie so this neutr sticks and curls around and at some point it starts to wiggling its way through the capillary tissue and one of the horizontal membrane to get across the tissue layers into the Airfield lung compartment and following this uh these white plus cells shown in red here chase the bacteria and fagin to clear and resolve the infection just like what happens in the living human Lo so nice thing about this model is that the because of the optical transparence of the device we are using uh it becomes possible to visualize and analyze uh the entire process of this very very phys complex physiological you know response in real time at higher resolution which would be very challenging to do using a traditional cell culture models or even in animal models okay so I think this model is interesting uh in the sense that the uh you know this system allows us to mimic complex physiological functions and responses and we also did uh nanotoxicology studies you know using this platform and so I just don't have time to talk about all these data but if you're interested you know please uh refer to the original science paper we published in uh 2010 but another really interesting aspect of this is um so using this technology we can start thinking about modeling uh comp disease processes in the human body so this is a a new research Direction my lab is currently working on focusing on um so just to give you a quick example uh when uh kidney cancer patients or melanoma patients receive this chemotherapeutic drug called interlukin 2 they often develop a complication known as pulmonary edema so edema is as you all know there's a fancy medical term for swelling and it's clinically defined as extravasation of intravascular fluid in the alv sex and in severe cases of pulmonary edema uh as a result of animetic reaction between plasma proteins and tissue factors Secret by inflamed cells you end up getting these blood cluts fibrant cluts within the AL AOS sex so very interestingly uh when this same drug is administered into the capillary channel of the long chip device so what happens is um as you can see here so liquid in the lower capillary Channel gradually leaks into the Airfield lung compartment and this channel becomes completely flooded uh within 3 to four days which is very similar to what happens in this patients developing ilt induced pulmonary edema we also see uh very extensive clotting actually the fibering clots you know forming on the surface of elv epithelial uh surface uh cells and so uh using the system uh we can you know mimic the uh these clinically relevant key pathological features of pul Edema induced by il2 toxicity and more recently we have also begun to uh investigate the adverse health effects of cigarette smoking using this technology so as you know you know smoking has decreased a lot over the two over the past two decades but in the United States alone 18% of the population still smokes so smoking induced or Associated lung injuries and diseases remain a very important Public Health concern in both the developing and developed countries so anyway uh so for this study what we're essentially doing is to smoke the cells in in Armic rutic devices so we're developing a smoking long on chip model for this study to investigate um smoking induced normal biological responses that happen in the small areas so the question is why small areas right so there's now very convincing evidence in in the literature that the these small sized bronchioles are a major set of tissue infection in inj uh injury inflammation and remodeling and they're thought to play a very important role in the pathogenesis and exacerbation of smoking Associated lung injuries and diseases but not much is known about what happens in the in this distal part of the lung that is very hard to access so just to tell you a little bit about the anatomy or structure the small area tissue consist of uh this columnar epithelium containing the ciliated cells and cl cells or Club cells and this epithelium is supported by this uh strumal tissue containing cells like fiberblast vasculature and macro phases so to mimic this uh three-dimensional structure uh post talking by La Dr Mark mandros has created a small are on a chip uh device which is shown here so this device has five layers and first of all to M make this estroma what we do is we fill this Middle Chamber with ECM hydrogel along with the human along fiber blast primary cells and also sometimes the macras and we also develop a special surface coating technique that allows us to very firmly anchor this ECM hydrogel to this polymeric surface uh to minimize and prevent gel contraction induced by cell generated contractile forces and this layer is then sandwiched between these two Chambers two channels lined with the primary human SM epithelial cells and primary human microvascular endial cells so this platform we can form this highly viable and fully differentiated primary human solar epithelium and this image also shows a very nice you know a stable and and physiological strumal tissue that we were able to form in this device and uh just for your information the green shows a cell deposited fibronectin we use type 1 collagen gel so we have evidence that these cells feel comfortable sitting in this m environment and they actually actively remodel their surrounding matrices in the long-term culture microptic device so this is how we you know culture these cells but for this particular project the more important question to be asking is uh how do we so this is how we do it so this is the smoking setup that Mark has developed and so we have a smoking machine that generates cigarette smoke in a very controllable fashion and the smoke is uh is humidified and diluted in this mixing flask to mimic physiological concentrations in the dist part of the lung and then the sample is delivered into the long a chip line with the cells so using this platform we are studying a various biological responses to uh cigarette smoke and we just don't have time to go into all the details here so I'll just give you very uh you know two quick examples so it's been pretty well established as you probably know uh cigarette smoking disrupts proteostasis and significantly increases protein misfolding or unfolding so when this happens uh ER and the plas reticulum which is a c organel responsible responsible for fixing these protein molecules gets stressed and that leads to something called UPR unfolded protein response so this is a very early response that happens very quickly so what we are showing here is as a result of smoking for a couple of hours uh these two UPR markers transcription factors get up upregulated significantly as you can see in these micrographs and in the longer term uh experiment what we see is uh we also found that that the cigarette smoke induces very significant remodeling of the strumal tissue in this model so this is what the strumal tissue looks like just to remind you green shows a cell deposited extracellular Matrix protein like a fibronectin but after smoking for a couple of days we start seeing these uh you know uh very extensive ECM deposition in within the stral tissue we also see increase cell proliferation and more interestingly we see two uh populations you know these fiberblast that kind of retain their typical spindly morphology but we also start seeing these polygonal cells uh in very extensive selective pericellular deposition around these polygonal cells so this is a uh this heroen is emerging Concept in fibrosis but it was very interesting to be able to see this in our you know in vut model anyways so these are some of the examples of biological readouts and responses that we can measure and analyze in this uh in this uh smoking lchip device okay so this I think uh the smoking or human long technology is is is interesting uh in the sense that it allows us to uh mimic both complex physiological and pathophysiological processes that happen in in the respiratory system so I think you know this is very exciting and it represents a major Advance uh from traditional cell culture models but what's more interesting to think about is um so we could you know potentially apply exactly the same biomic the ocular system from the external environment and it e we use 3D printing technology to make these a 3D Dome shaped cell culture scaffold with the same curvature as the human cornea and to mimic the other tissue layers what we do is um we first thing we do is we inject ECM hydrogel precursor solution along with primary human cateyes into the cavities within the scaffold to kind of replicate this strumal layer and we also uh developed the uh the 3D cell patterning technique uh that allows us to form this physiological concentric tissue pattern with coronal cells at the center surrounded by the conun tal cells and for culture we you know see the device grow them uh to comp monolayers and then we expose them to air to induce a differentiation which is very similar to Long cell culture and as as a result of differentiation these corneal cells that uh start off as a single layer become stratified uh forming multiple layers they form tight junctions upregulate uh epithelial markers and we also confirm that the differentiation of conjunct Tyle cells cells into gobl cells and then we uh combine this with this electromechanically actuated soft hydrogel eyelid layer to mimic blinking motions so as you can see here we inject artificial tier fluid into the channel it gets secreted and picked up by this sliding eyelid and then gets spread on the on the surface so here we're showing that even after repeated cycles of actuation blinking actuation cells remain adherent and viable on the scaffold surface but the reason why this is important is because this is the mechanism that allows us to form physiological TI film on on the surface of the scaffold so to me to validate this uh we use this instrument called ooc so this is a clinically used instrument that allows opthalmologist to measure tier fluid in human patients so what we did was uh to mimic the uh to measure the thickness of tier fluid layer in our device and it was measured to be around 15 microns and the physiological tier film thickness ranges from five up to 20 microns so we were able to show that this device allows us to form a physiological tier fluid so I guess I'm running out of time but uh so I'll just very quickly mention this and so we're actually leveraging this technology to develop platform for screening acute toxicity of chemicals and also we're uh uh using this platform to model complex ocular diseases like DED so uh I'll just skip this um in the interest of time and we're also devel uh doing a lot of work uh in the area of reproductive biology and Medicine uh so this is an area that I think has traditionally suffer from a lack of human relevant human relevant predictive models and so we're very excited about the possibility of leveraging this technology to contribute to research activities in this area so for this uh we're developing reproductive organ onip models and recently we published a paper about papers about placenta honor chip and we're also developing cervix hono chip and so uh if you're interested you know uh please refer to these papers here okay just to quickly quickly wrap up uh we are developing these microengineered physiological culture devices uh that allow us to mimic the essential structure and function of uh of the functional units of human organs for a variety of applications and we think that the uh these models have great potential for a variety of applications you know just to quickly tell the impact that you know our work has made uh so for example the human breathing laip technology actually uh had a major impact and it changed the way Regulatory Agencies and funding agencies thought about invital testing and became one of the most important reasons why they started new funding programs and President Obama you know made an announcement five years ago uh highlighting major plans to support research activities that are focused on developing these microf physiological systems for screening for more efficacious and safe drugs in PL in preclinical Trials so we feel very you know good about that but more importantly you know we as bioengineers uh bi biologist or medical scientist you know working at the interface between biology engineering and medicine will have a lot to offer in this very exciting new area so just a quick mention you know we also started a company uh based in uh Boston it's called emulate uh they're translating and commercializing this organ own technology in partnership with the pharmas and Regulatory Agencies like FDA and I also gave a tedex talk last year to talk very specifically about what this technology has to offer in terms of improving the current D Discovery Pipeline and we recently also wrote a review uh on a similar topic uh for nature review stru Discovery in case you're interested okay with that I like to end and um I'd like to thank my group and also uh funding sources and uh with that I like to end and be happy to take any questions uh you might have thank you okay thanks very much Dr ho and and Dr bar as well certainly some really exciting work going on in both of your Laboratories we do have a few questions um uh for let's see will start um actually this for Dr Hu um for the long on chip can we use modeling Andor reverse do symmetry to predict external doses that will cause lung injury observed in this invitro system for specific chemical toxicants so um what external factors I I think I missed the first part uh can you repeat the question sorry sure can can we use modeling and or reverse do symmetry to predict external doses that will cause injury observed uh Yes actually challenging task and you know so in our case uh in our experiments uh our doses were based on uh the values we found in the literature but for uh for determining you know uh optimal doses for you know for injuries or for uh for treatment I think you know what we would have to do is to kind of you know uh leverage this technology in conjunction with the uh you know the computer simulation models like modeling approaches like you know uh PK to figure out you know uh the resonant times you know for drug compounds in each compartment organ compartment and and also U there are many factors we should consider uh to determine you know optimal doses for treatment or uh to find out you know the uh the the toxicity uh you know caused by you know overdose actually overdosing the drug so um so we haven't actually tried that in in myab but you know other groups e e e May yep yeah if you look at um on the slides there prisic at all um that's for the 2011 paper that about the micro lung model but I'm sure as Doctor Who knows you get styed with um you know the um the IP and it's taken for a long time for the metabol lung we haven't been able to publish that yet we've just secure you know the patent and everything so the university is really wary about me writing anything so I have to you know just do a little cursory review papers and things like that but then but Zoe's paper the 2011 um you can read that and you'll be able to um build the model yourself or you can buy you can license we can license your technology as well sure okay great thanks very much um well that concludes the the questions that have uh come in via the chat box um so with that being said I'd like to again thank uh Dr baray and Dr Hu for their participation today this was the sixth and final webinar in a series on alternative approaches for acute inhalation toxicity to address Global Regulatory and non-regulatory data requirements we had over 500 reg registrants for this series so we're really pleased with the the interest and the participation in this series and certainly uh as you can see on the screen there are hyperlinks where you can find more information on this on on this uh Series in total as well as on the Fisk website access to the recordings of each of the webinars so that being said thank you very much and have a nice day thank you thank you bye thanks bye
Up Next
Real-Time TEER Monitoring for Organ-on-Chip Barrier Integrity
@Dynamic42
126 views•2025-05-05

Graphic Medicine: Comics for Collaborative Healthcare Communication
@nationalpatientadvocate
189 views•2023-12-04

Neuroanatomy: Central and Peripheral Nervous System Divisions Explained
@AKLECTURES
136.2K views•2014-09-20

Stages of Labor and Vaginal Birth | Childbirth Animation
@nucleusmedicalmedia
52.1M views•2017-08-18
Related Study Plans & Knowledge Roadmaps
Structured learning paths in Medicine