

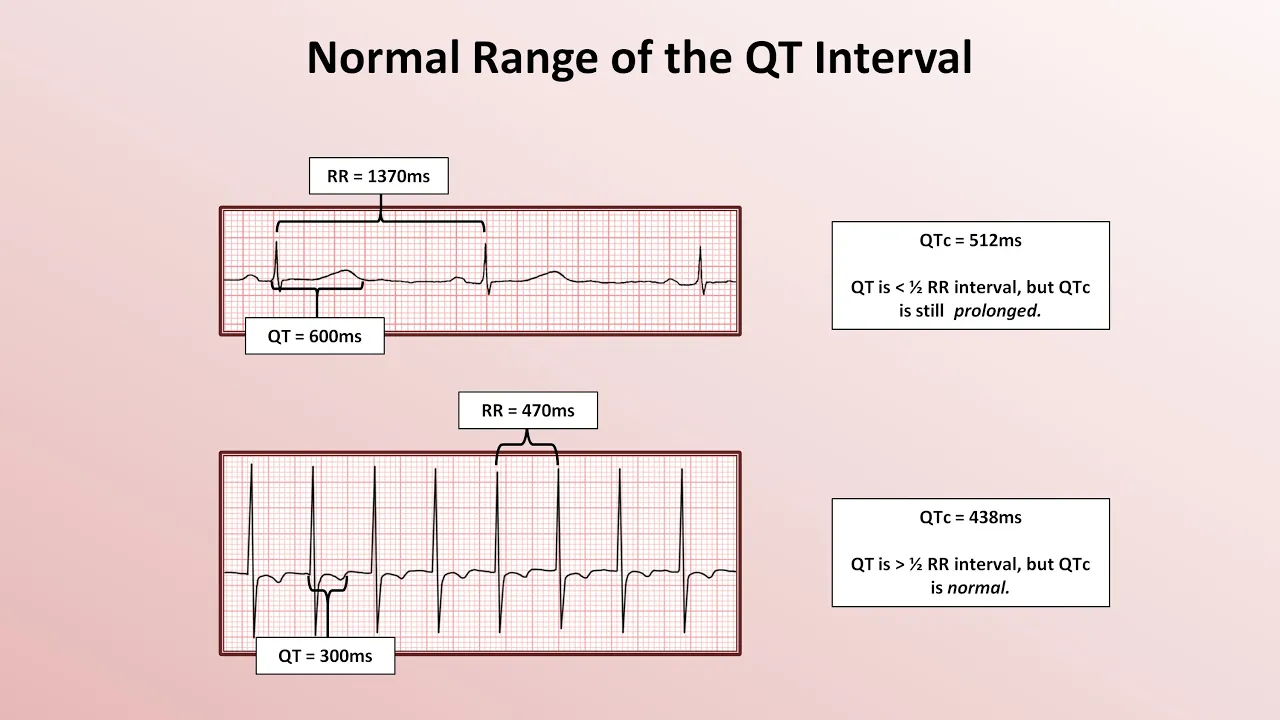









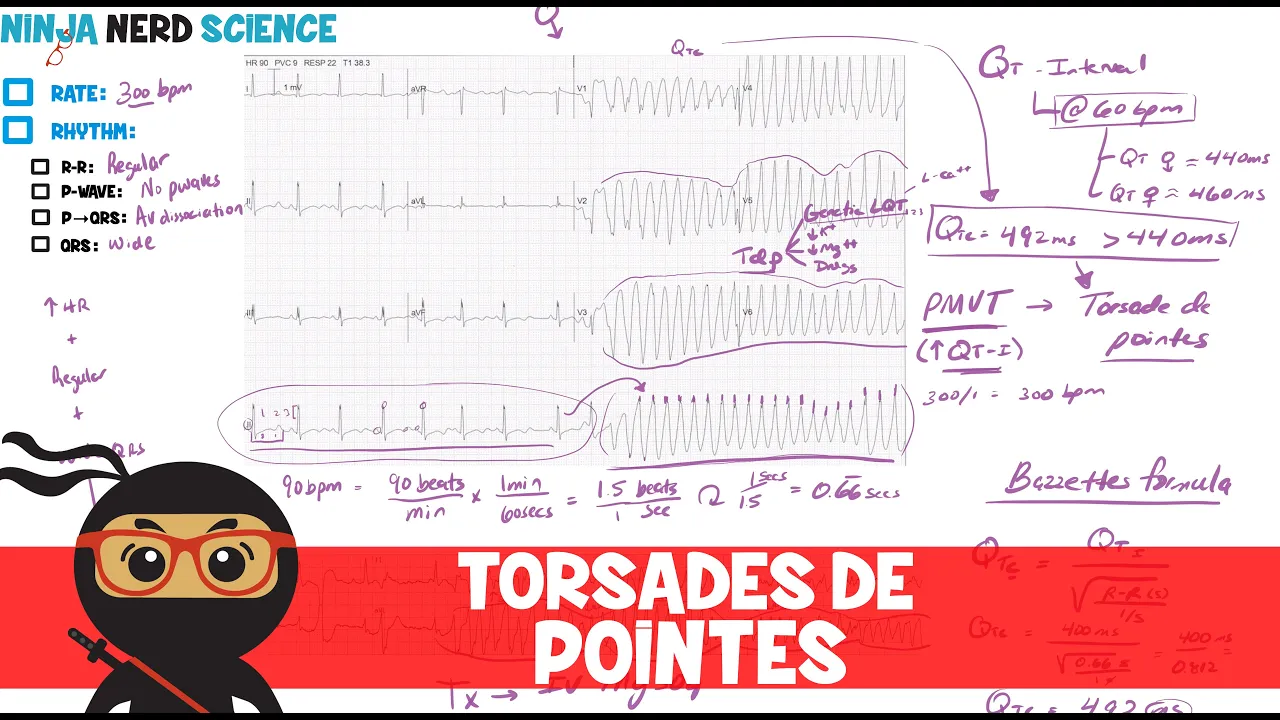










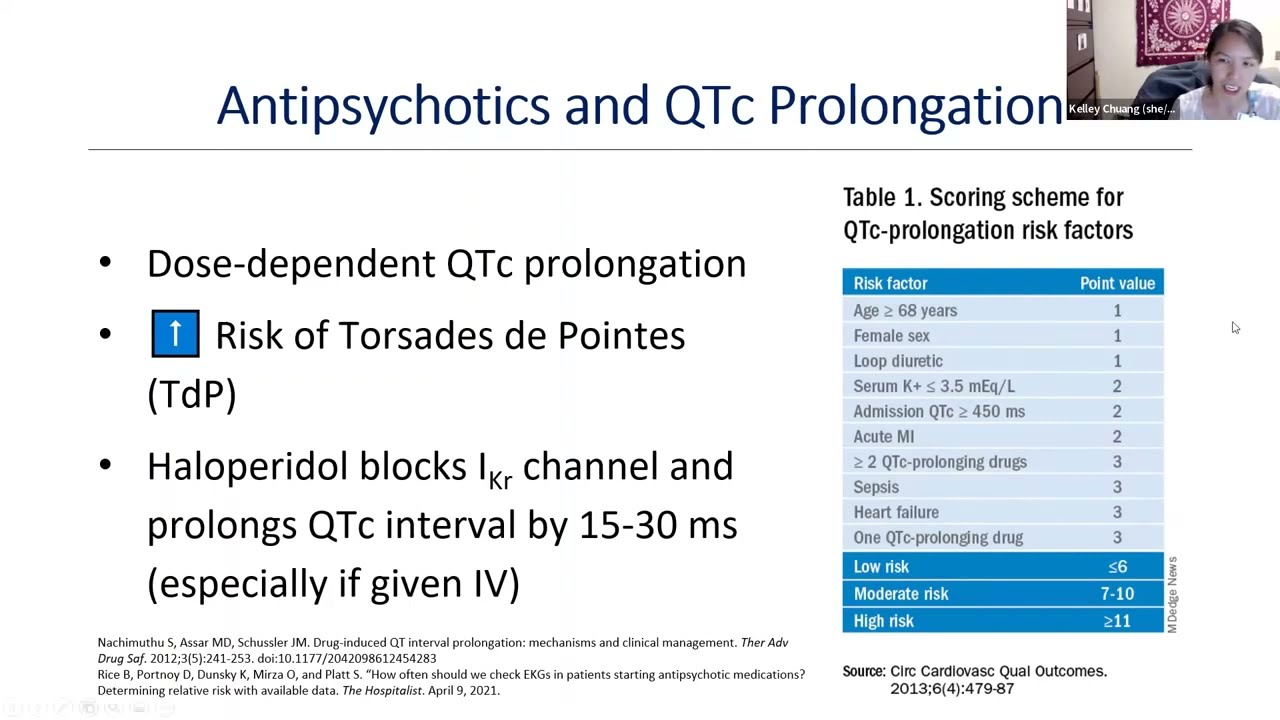




First-generation antipsychotics, particularly low-potency phenothiazines (chlorpromazine, mesoridazine, thioridazine) and haloperidol, carry the highest risk for QTc prolongation and torsades de pointes, while second-generation agents like ziprasidone and quetiapine also show significant QT-prolonging effects; however, aripiprazole and lurasidone demonstrate the lowest QTc prolongation risk among antipsychotics, and clinical management should include baseline EKG monitoring for high-risk patients and careful consideration of cumulative drug doses when prescribing multiple antipsychotics.
Antipsychotics and QT Prolongation: Risk & Prescribing Guide
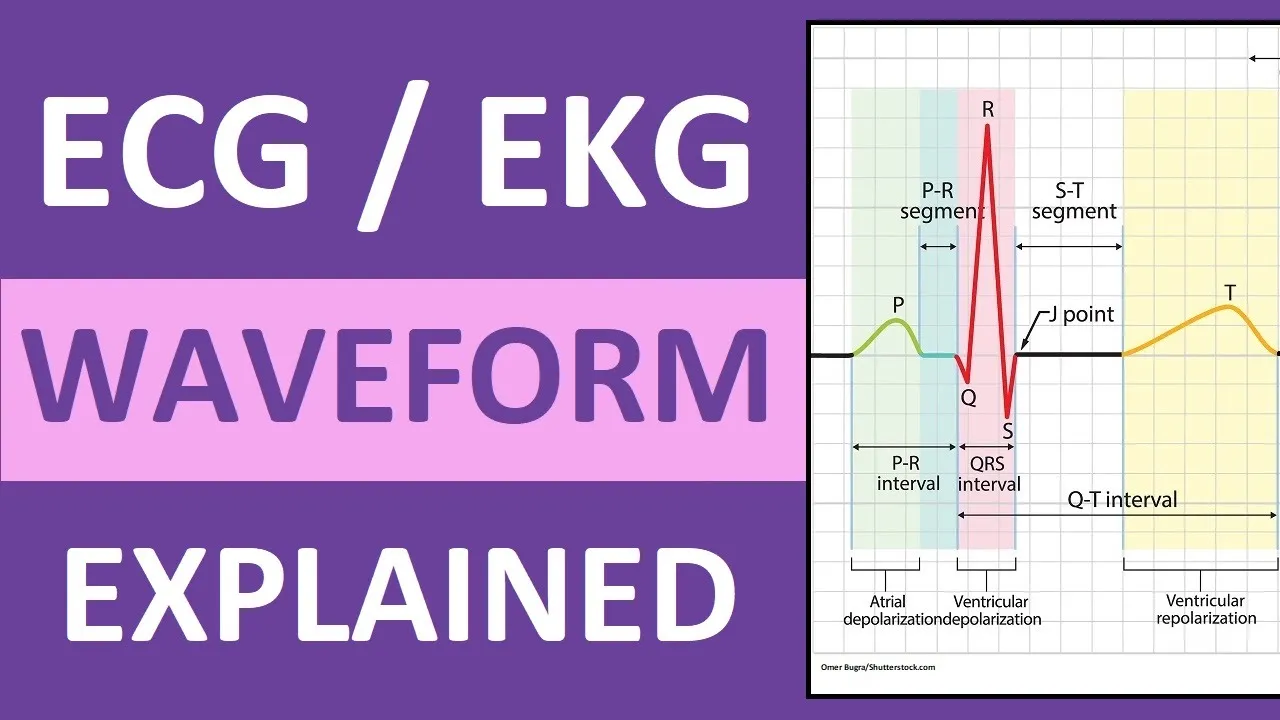
Added:Understanding cardiac electrophysiology, specifically the components of an electrocardiogram (ECG) and what the QT interval represents clinically.
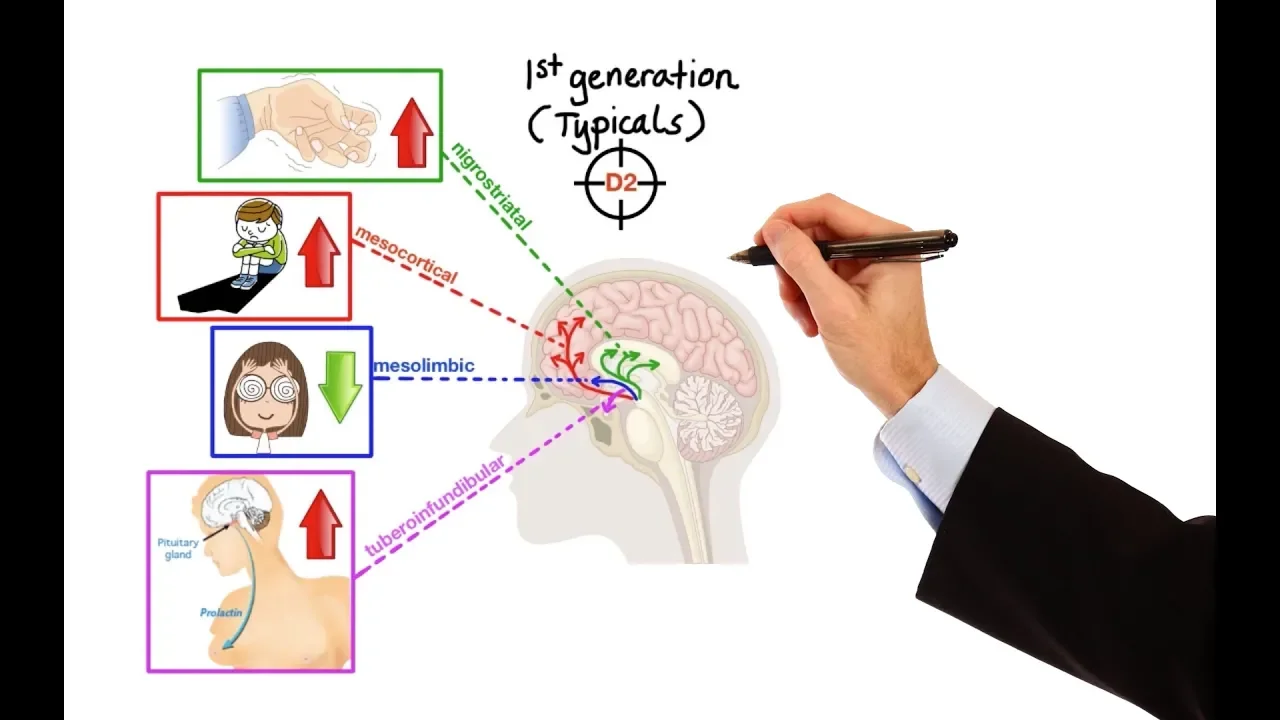
Basic pharmacology of antipsychotic medications, including the distinctions between first-generation (typical) and second-generation (atypical) antipsychotics.
The physiological mechanism of cardiac ventricular repolarization, particularly the function of potassium ion channels (such as the hERG channel).
An introductory understanding of Torsades de Pointes (TdP) and why it is a critical clinical concern.
Advanced emergency management protocols for drug-induced Torsades de Pointes (TdP), including the clinical use of intravenous magnesium sulfate.
Evaluating complex drug-drug interactions that synergistically increase QT prolongation risk, such as combining antipsychotics with certain antibiotics or antiarrhythmics.
Application of clinical risk-stratification models (like the Tisdale score) to predict QT prolongation in patients initiating psychotropic therapy.
Investigating the pharmacogenomics of drug-induced cardiotoxicity, including how congenital long QT syndrome or CYP450 enzyme polymorphisms affect patient risk.
5.9K views108likes7:40Original Release: 2019-07-23
in this next section we're going to talk about antipsychotics and their association with QT prolongation and we'll start by talking about first generation antipsychotics so the low potency phenothiazines which include medications like theory design chlorpromazine and Mesirow design are the first generation antipsychotics that are most associated with QT prolongation and as a class first generation antipsychotics are linked to greater duty prolongation than our second-generation agents but it's important to recognize that this effect is primarily driven by those low potency phenothiazines in terms of the risk for tore sod the difference between first and second-generation antipsychotics does not appear to be statistically significant in addition to the low potency phenothiazines the other first-generation antipsychotic that is most commonly associated with QT prolongation is haloperidol the association of haloperidol with QT prolongation though remains somewhat controversial a recent meta-analysis found that the effects of haloperidol on the QT interval are actually very similar to several second-generation antipsychotic agents that being said there are other studies that suggest a greater risk for ventricular arrhythmias or sudden cardiac death with haloperidol one of the forms of haloperidol that has been most associated with QT prolongation and tore sod is the intravenous form there have been 70 cases total reported to the FDA 58 of those involved QT prolongation 54 of those involve tor siddhappa it's important to recognize though that almost all of those cases had other significant risk factors for QT prolongation 32 of the patients had underlying cardiac conditions and 39 were on other agents that are known to prolong the QT interval so the association of intravenous haloperidol with QT prolongation or tor saud does remain somewhat controversial and there is not strong evidence that intravenous haloperidol separates out from oral or intramuscular haloperidol with regards to second-generation antipsychotics ziprasidone is the agent that most people associate with QT prolongation in 2002 the FDA issued a blackbox warning for as a president urging prescribers to avoid use in combination with other QT prolonging agents or in patients with a history of cardiac arrhythmias the average QT prolongation with the president is somewhere between 10 to 21 milliseconds but up to 20% of patients experience an increase greater than 60 milliseconds and in a meta-analysis that compared all of the second-generation antipsychotics as well as a couple of the first generation antipsychotics tsipras adone actually performed the worst in that study it was similar to illa Paragon but slightly worse another agent that sometimes highlighted in this discussion is quetiapine and that's because in 2011 the FDA strengthened the warning around quetiapine and recommended that it be avoided in use with other QT prolonging agents in patients with a history of arrhythmia or in patients with metabolic deficits who may be at increased risk for QG prolongation in general it's felt to have relatively mild effects so there is some suggestion that up to 20% of patients experience a prolongation of greater than 20 milliseconds which is considered more clinically significant among the second-generation antipsychotics and really among antipsychotics as a whole the agents that perform best from the standpoint of QT prolongation appear to be aerosol and larezo Doane most other antipsychotics can't really be separated out from one another and end up somewhere in the middle of the pack and this includes olanzapine risperidone and clozapine another issue that has generated some inquiry in the recent past is the idea about whether polypharmacy with multiple antipsychotics leads to greater QT prolongation there's unclear conclusions regarding that but there's speculation that if that is true it's probably mediated by the total cumulative dose or the total cumulative relative dose rather than by the fact that the patient is on multiple different agents so when we're thinking about antipsychotics as a whole and their impact on QT prolongation we can do a little bit of risk stratifying with regards to specific agents though it's pretty challenging we think that agents that convey a minimal risk include air peppers on larezo dome and we think that agents that convey a higher risk includes a presiden illah parrot own theory design and possibly intravenous haloperidol practically speaking how do we think about using antipsychotics and patients who may be at risk well for intravenous haloperidol in particular in the inpatient setting it's generally recommended that prescribers check a baseline EKG and at least one follow-up EKG it is important though to minimize other risk factors for QT prolongation in that setting and that includes repeating electrolytes specifically magnesium and potassium should be repeated 2 2 & 4 respectively on a daily basis and minimizing other risk factors which may include looking at other medications that the patient is taking which might either independently increase the risk for QT prolongation or interact with haloperidol in such a way to convey a greater risk and seeing whether there's room to minimize or mitigate those other risk factors in patients who have a QT greater than 500 milliseconds you might want to consider adjunctive agents for managing the delirium in the hospital when we think about using antipsychotics in the outpatient setting we generally don't recommend monitoring for patients without risk factors unless they're being prescribed one of the high-risk agents such as theory is a president or a perdón there's really not evidence to monitor patients who are being started on a different and a psychotic who don't have significant risk factors on the other hand for patients who may have multiple risk factors for QT prolongation it might be worthwhile to obtain an EKG at baseline and intermittently after the initiation of an antipsychotic just to mitigate against the risk so to summarize some key points from this section theory designs of Presiden and illa perdón are the antipsychotics associated with the most QT prolongation intravenous haloperidol has been associated with QT prolongation and tor sod in various case reports though it appears to be a very rare occurrence and it's important to remember that intravenous haloperidol is often prescribed to the sickest patients in the hospital which may confound the association aerosol and larezo don't appear to have the least association with QT prolongation among the antipsychotics and are generally considered safe in this regard
Up Next
4:28
Acute Dystonic Reaction Management with Diphenhydramine
@lmellick
1.2M views•2012-01-19

37:45
Rapid Quantitative Immunostaining of Intact Biological Systems
@simonscenterforthesocialbr1919
247 views•2015-12-02

10:28
Neuroanatomy: Central and Peripheral Nervous System Divisions Explained
@AKLECTURES
136.2K views•2014-09-20

3:05
Stages of Labor and Vaginal Birth | Childbirth Animation
@nucleusmedicalmedia
52.1M views•2017-08-18
Related Study Plans & Knowledge Roadmaps
Structured learning paths in Medicine
medicine
Interpreting PFTs: Spirometry & DLCO
01Respiratory Anatomy and Physiology Foundations
02Spirometry: FVC, FEV1, and Flow-Volume Loops
03Lung Volumes and Plethysmography
+ 2 more learning modules
12h5 modules
Explore Roadmap
medicine
Abnormal LFTs: Diagnostic Workup & Pathology
01Liver Anatomy and Basic Physiology
02Introduction to Liver Function Tests (LFTs)
03Hepatocellular vs. Cholestatic Patterns
+ 3 more learning modules
12h6 modules
Explore Roadmap
medicine
Analyzing Blood Smears: RBC, WBC & Platelets
01Introduction to Blood Components & Smear Preparation
02Normal Morphology of Blood Cells
03Erythrocyte Pathologies & Morphological Variants
+ 2 more learning modules
12h5 modules
Explore Roadmap
medicine
Mechanical Ventilation: Waveforms & Alarms
01Anatomy and Physiology of Breathing
02Introduction to Mechanical Ventilation & Core Modes
03Ventilator Settings and Waveform Interpretation
+ 2 more learning modules
12h5 modules
Explore Roadmap