
































Moral hazard in healthcare insurance can be controlled through four main policy tools: (1) Cost-effectiveness analysis, which evaluates treatment options to maximize health outcomes per dollar spent but may be politically controversial; (2) Cost-sharing mechanisms like deductibles and co-payments that make patients more cost-conscious but can reduce affordability and equity; (3) Gatekeeping and queuing systems that require patients to see primary care physicians first, which can limit specialist access and create wait times but may be more equitable than cost-sharing; and (4) Prospective payment systems that pay fixed amounts based on diagnosis rather than services rendered, which incentivizes cost control but may create adversarial doctor-patient relationships and potentially compromise care quality. Each approach involves trade-offs between efficiency, equity, and political feasibility.
Controlling Moral Hazard in Health Insurance: 4 Policy Tools & Tradeoffs
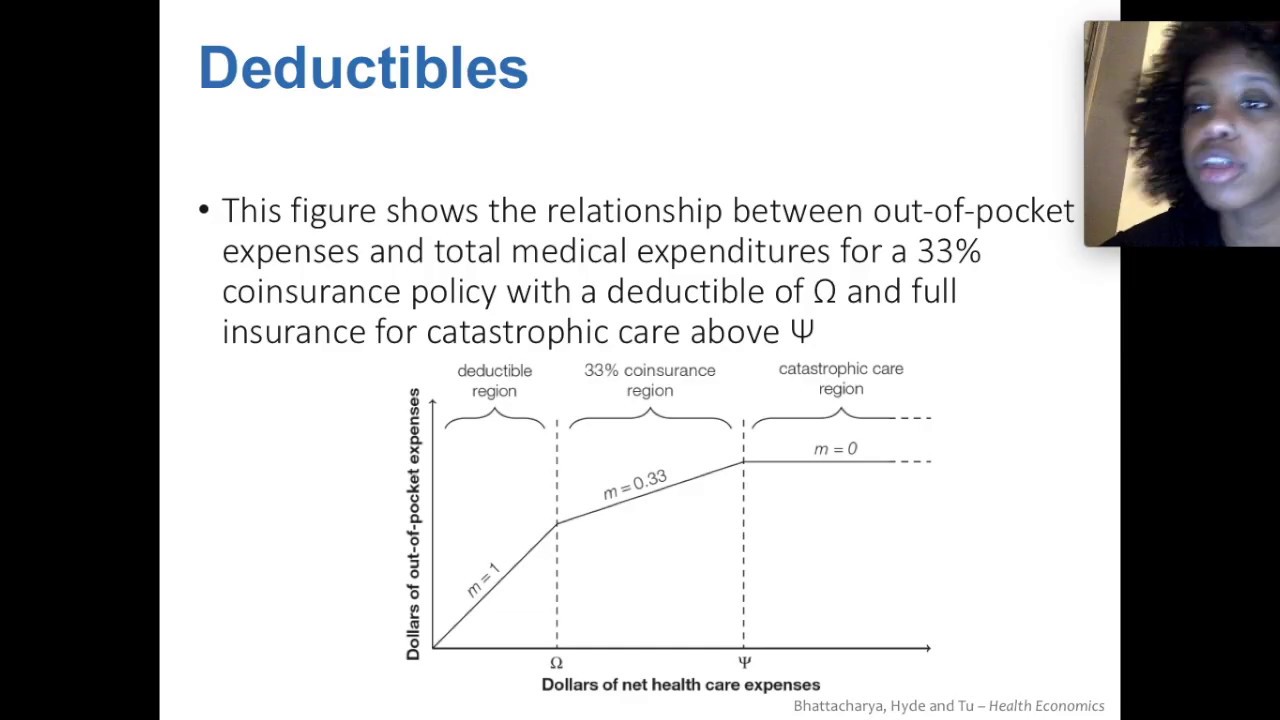
Added:so how should moral hazard be controlled in the private market private insurers just offered different levels of coverage and you decide which one to purchase how much coverage you want versus how much moral hazard control you want but when it's the government in the insurance market it's the lawmakers and the policymakers who have the responsibility of these tough decisions and different ways of addressing moral hazard can be pretty controversial and politically difficult to do policymakers don't have a graph like the one that we used in Chapter chapter 7 to understand you know the curvature of the individual utility distribution and to know how much coverage is you know going to be utility maximizing for a given individual instead they have these different tools for addressing moral hazard and we've talked about all of them health Technology Assessment cost-sharing gatekeeping and queuing or lines and also prospective payment systems so one of them it's cost-effectiveness analysis that's the health technology assessment and what that means is just gathering information about different kinds of treatment options to determine which of those treatments produces the most additional health for the least cost so it reduces spending on inefficient and costly treatments but it also makes the insurance contract in a sense less full for the people covered that trade-off might be worthwhile though because it makes the entire system cheaper for example in the UK they have the National Institute for clinical effectiveness called nice which determines certain cancer treatments that are not going to be funded in the public system in the national health system so the problem is that denying coverage for some treatments could be really politically unappealing there was the phrase death panels that came out with the Affordable Care Act even though they weren't actually implementing any cost-effectiveness decisions in the law it's still just politically it's like a really good sound bite I suppose so in the US so we talk about in the UK how they do implement clinical you know CEA in their decision-making but in the u.s. actually Medicare is forbidden by law from implementing any cost-effectiveness analysis and its decisions for treatment they cover anything that is considered medically effective regardless of its price so that's good because you don't have to make those gut-wrenching decisions about how to treat sicker patients but also it allows moral hazard to flourish another option is cost-sharing so these are the out-of-pocket costs that insured people pay when they receive health care deductibles coinsurance rates and co-payments that you pay when you see a doctor cost-sharing appears to be more politically palatable in the United States than cost-effectiveness analysis decisions but it can make health care less affordable for patients and in this way undermines equity so for example Medicare does allow cost-sharing it does not cover the full patient cost for health care so as of 2012 Medicare enrollees had to pay the first little more than $1,100 for a hospital visit and 140 of outpatient expenses and they have to pay two hundred and eighty nine dollars per day after the first 60 days of a hospital stay these kinds of things they they're intended to force enrollees to economize but it also leads people to just purchase supplemental private insurance that covers the gaps that Medicare doesn't fully cover another option is gatekeeping and queuing or lines it's a European textbook so gatekeeping it's like this tiered system of doctors that you have to visit in order so it keeps costs down by eliminating frivolous appointments and focusing limited resources on patients who truly need the care so if you have to go and see your family doctor first before you're allowed to be referred on to a specialty let's say dermatology so doctor the primary care physician might cost less and be able to treat it just as well so it kind of it can limit the total number of specialists available because specialists cost more for the system but when demand for those specialists outstrips the total supply of specialists you can end up with wait times or queues so they kind of go hand in hand usually having a long wait is an indication of a market inefficiency it means that there is not enough supply to meet demand but if there is moral the moral hazard its present then it might actually just be a reflection of overly inflated demand for specialists in that case limiting the number of specialists couldn't save money without sacrificing house so if the primary care physician is just able to treat whatever your illness is then we can limit those specialists without in adequately meeting your healthcare needs so the hassle of waiting for a specialist can be a type of a non-financial cost that patients have to pay but paying through wait times or queues can be a more equitable way of allocating scarce resources compared with cost-sharing where because if rich and poor alike are all waiting in the same line then wait times can be you know a more equitable way of deciding who's going to get the care as opposed to whoever can afford to pay so they can be more equitable like wait wait times can be more equitable than cost-sharing but having those wait times also risks provoking a political backlash another option is prospective payments so the traditional way for paying for healthcare is retrospective payments in that case the payment is made after the service is rendered and the payment depends on how much healthcare you received so how many tests did you get did you get an MRI any lab work you know etc and then the payment is based on all the things that you got that's a fee-for-service system they pay a fee for each service that you have and the doctor has no reason to deny a patient a service that they wanted based on costs if fosters trust between patients and physicians but it also can create a system for physician induced demand where physicians are kind of just ordering extra tests that you might not have needed the alternative is the prospective payment system which can be implemented as a way of like alleviating moral hazard in that case payments are made before the healthcare is delivered and consumed and the charge is based not on all of the different tests or procedures that were performed but instead on the diagnosis or the condition of the patient when they were admitted so under a prospective payment system for example a patient who is you know brought into the hospital for a heart attack is paid a fixed amount for every heart attack person every heart attack patient you know maybe based on their other comorbidities or other illnesses that they have as well that gives the hospital an incentive to economize because if they can provide care that cost them less than the amount that they know they're going to receive then sometimes they get to keep the difference so it's an incentive to for hospitals to not just like do every single possible test a lot of governments around the world have been embracing prospective payment systems to reduce moral hazard and physician induced demand but it can also turn that doctor-patient relationship kind of adversarial where patients are seeking treatments that maybe their providers are not authorized to provide like that their doctor you know maybe the hospital tells the doctor that they shouldn't be running all these tests because the hospital wants to save money but the patient wants it and that kind of puts the doctor in a difficult position in one study after Medicare implemented prospective payment system in 1984 mortality increased significantly for that subset of hospitals in the months after their transition into this prospective payment system you know because it kind of incentivizes hospitals to cut corners as well so there are these four different ways of control world hazard and each of them really has its trade-offs in the next video we'll talk about how the provision of healthcare and healthcare providers should be regulated
Up Next

Economic Leakage in Tourism: Causes & Solutions
@TourismTeacher
7.7K views•2022-03-11

Tiebout Model & Club Theory: Local Public Goods | Public Finance
@Vidyamitra
12.6K views•2016-04-14
Health Insurance Cost Sharing: Coinsurance, Copays & Deductibles
@hpam621healtheconomicscuny8
999 views•2020-03-03

The Age of Easy Money: Fed & Inflation | Full Documentary
@frontline
21.2M views•2023-03-15
Related Study Plans & Knowledge Roadmaps
Structured learning paths in Economics