










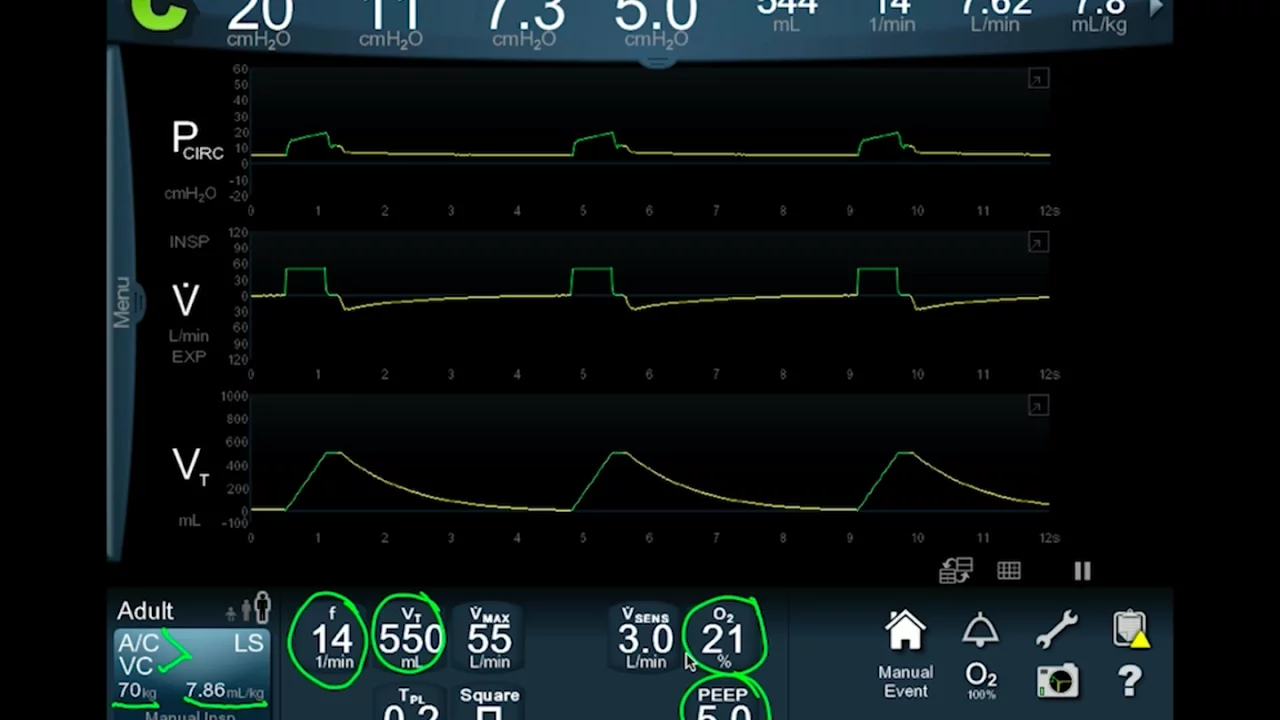












The respiratory system operates through interconnected pressure gradients: airway pressure, alveolar pressure (measured as plateau pressure), pleural pressure, and transpulmonary pressure. Ventilator waveforms—pressure-time, flow-time, and volume-time scalars, along with pressure-volume and flow-volume loops—provide critical clinical information about respiratory mechanics. Static compliance (measured during inspiratory hold) reflects only elastic properties, while dynamic compliance incorporates both resistance and elasticity. Pressure-volume loops reveal inflection points: the lower inflection point indicates minimal pressure needed for adequate alveolar recruitment, and the upper inflection point signals overdistension risk. Understanding these principles helps clinicians optimize ventilation settings, detect complications like auto-PEEP, and minimize ventilator-induced lung injury.
Mechanics of Ventilation: Pressure, Flow, Volume & Waveforms
Added:okay all right so um there are a lot of relevant pressure gradients and pressures in the respirator system but I'm just going to try to uh incorporate whatever are relevant uh in understanding this topic so we have the airway pressure which is the atmospheric pressure labeled as p a wo um and it's usually zero or atmospheric and then we have the alveolar pressure which we measure clinically as a plateau pressure this the normal indiv idual who are not ventilated is about minus5 cm of water so as we can see there's a pressure gradient of 0 to 5 that allows the flow of this gradient is created by the inhalation uh inspiratory process and allows the uh flow of gas from the Airways to the alvioli now the gradient between the airway pressure Pao and the Alvis is known as the trans airway pressure and we also have a plural pressure which is clinically not monitored but we can use an esophagal monitor to uh which provides a decent correlation to the plural pressure um that as we saw is is plays a crucial part in um in allowing ventilation the gradient between the alveolar pressure and the plural pressure is known as the transpulmonary pressure so the trans airware pressure essentially is a pressure that must be generated to overcome the resistive forces of the airway and the trans ponary pressure is basic is the pressure that's required to keep the alvioli distended and this is known as the alveolar distension pressure as well so to review the basic mechanics of spontaneous ventilation the inspir inspiratory muscle does um results in a negative plural pressure that starts off um at minus5 generally and through the course of inspiration goes up to- 10 cm of water this negative int plural pressure results is transmitted to the Alvi which are which become more negative and thus you have the gradient formed between the upper Airways and the alvas with inhalation at the end of inhalation when flow stops um and the elastic recoil of the chest wall as well as the lungs enable uh result in decrease in these plural pressure which is transmitted to the alvioli and thereby air is exhaled out now let's contrast this to a patient that's on positive pressure ventilation here air flow is generated to the ventilator and is directly flow and as a result of the positive pressure it gets transmitted into the alvioli this results in the plural pressures becoming more positive and the chest and lungs expand once the ventilator ceases to provide a flow um the elastic recoil of the chest wall and the lungs now caus the plural pressures to go back low and is once again transmitted to the alvas and air is passed out so if we are to look at the respiratory system in a simple fashion you can think of it as two forces one is the resistive forces which is depicted here by an air pump and tubing and then the lung forces which are the elastic forces uh we can think of those as spring coil now this is a very simple model but it helps us understand the mechanics involved in a ventilated patient um because it helps us understand the interactions between pressure volume and flow so this system here if we apply Newton's law of third law of motion which says all forces have equal and opposite reaction we have the force that's applied to the ventilated ventil by the ventilator into the respirator system so force is pressure over a period of time is equivalent to the elastic pressure and the resistive pressure to explain this a little bit more so the ventilation pressure is p and elastic pressure is the pressure that's required to inflate the lungs and the chest wall against those spring coils and the resistive pressure is the pressure that's required to move the air through the resistive Airways the ET tube the upper Airways so elastic pressure is change in volume times it's the elastic property known as the elastins which is e and the resistor pressure is flow so we know from basic phys that flowtimes resistance is pressure in pulmonary compliance is a better used term or more commonly used term than elastin compliance basically means how easily it is to um stretch something what elastin is the opposite of it so compliance is one over elastin so when we replace this into this formula we get basically a press relationship between pressure change in volume the compliance of the respiratory system flow and the resistance of the Airways so why am I going over grade four physics because when we understand pressure air flow and volume measurements um these quantify basic mechanical properties of the respiratory system and with these three basic principles we are we can understand resistance compliance and work of breathing these individual parameters along with graphic displays from ven vators helps us understand um the how how patients being ventilated and as well as assess problems that occurred during ventilation so when we think of mechanics of ventilation it can be static mechanics or dynamic mechanics static mechanics are mechanical properties that occur in the lungs during no Flow State so essentially a pause in air flow occurs and then um measurements are taken to assess the compliance of the the respiratory system Dynamic mechanics are the mechanical properties that occur during a stable flow or variable flow in the respiratory system we obtain datas about resistance and compliance through sampling various flows and volumes in the respiratory system and by using mathematical models such as the leas square ma uh Le Square fitting models we're able to um compute an overall um graph of the mechanical uh properties of the lungs so to understand um these mechanical properties of the lung um these datas provided by the ventilators we have to we have to have some basic understanding of scalers and Loops that are provide that that scalers and loop data that the ventilators provide us so scalers are variables of pressure flow and volume plotted against time while loop are variables of pressure and volume or flow and volume plotted against each other so I'll be going over each one of these um through the course of my talk but um very briefly all these IND all these measures helps us um has a lot of clinical utility one it helps us understand what the mode of ventilation is um it helps us set of Peep and understand what the level of Auto peep in a um in a system is uh we can adjust volumes and uh optimize management based on these weight forms so pressure scalar pressure scalar is a pressure to time graphing which shows a gradual change of pressure over a period of time now traditionally it was achieved by am monometer that was placed at an airway opening in a ventilator but modern ventilators have have it Incorporated within the ventilator to the right of the slide is a sample pressure time scale uh graph now this is in a volume controlled ventilation so there are certain key elements of these graphs so pressure is on the Y AIS and time is on the x-axis if a patient initiates a breath it's depicted by a negative uh infle a negative um inflection in the scale and then if there are no patient assisted breath it starts at a baseline of zero if an auto peep is present line starts at the set peep sorry not Auto peep set peep the next Landmark on this graph is the peak which is the peak inspir pressure and as we're going to see Peak inspir pressure is influenced by Airway resistance and compliance and then with an inspiratory pause where there is no flow we achieve the plateau pressure and Plateau pressure is a reflection of chest and lung resistance as well as the pressure in the small air Airways and alola so this pressure um waveform starts at a baseline point a um here and as pressure is gener as flow is generated the pressure rises in the system from point A to point B now this pressure is due to is to overcome the resistance and the air waves so it can be calculated um by the known resistance and the flow gives us an idea of the pressure required to generate this pressure uh for air to flow from point A to point B and uh following that the gradient pressure curve moves from point B to point C here this is the pressure um that is required to overcome um this is the pressure um that is needed to um to move volume uh against the Alvar distension pressure and over a change of time um this change in pressure over a period of time is a reflection of flow as opposed to the compliance of the respiratory system and at Peak inspiratory pressure which is point c um uh flow stops in from the ventilator if we are to initiate um inspiratory hold flow will drop the pressure will drop from C to point D if one thing we can notice here is the change in pressure from point A to point B is similar to the change in pressure from point C to point D so this is so they they follow they fall in parallel following a sufficient inspiratory hold um because of leak in the airway system as well as further recruitment of valvi pressure Falls from point D to point e which is the plateau pressure and Plateau pressure is can also be calculated by the change in volumes and the compliance of the respiratory system following at this point when the ventilator stops providing a flow exal exale um uh the um pressure Falls further to point F which is at the beginning of the next cycle and the overall change in pressure in the system is reflected by resistance times the expert Tre flow in pressure controlled ventilation the waveforms are different as the in Peak inspiratory pressure is set is the preset value that we have the pressure always starts at the lower point which is here at the peep or or lower defined pressure and Rises steadily to the peak inspiratory pressure and stays that pressure through the course of the time of inspiration which is usually set by clinicians and at the end of that inspiratory time pressure drops rapidly down to the Baseline and remain so till uh initiation of the next inspiratory cycle so um one thing we can see from that from the difference between this graph and the other one is as pressure is preset in pressure control ventilation the pressure time diagrams don't generally help us are very don't really provide us with too much information about resistance and compliance of the entire system in pressure controlled ventilation to look at um this is the graph from the volume control ventilation of pressure time scalar just wanted to go over some key points that I went over earlier this change in pressure point from A to point B is the trans airway pressure which we went over earlier and the elastic properties of the rist piure system is the slope of this line from this point a to the plateau pressure and the trans aware pressure is generally um a difference between Peak inspiratory pressure and Plateau pressure and the alol pressure is reflected by the plateau pressure here so the clinical application of this is when compliance change Peak and Plateau change together because it's a reflection of the airway pressure as well as compliance of the resist the compliance of the change in the comp um it's a change in the airway pressure as well as sorry the resistor pressure as well as the compliance pressure so with decreasing compliance Plateau increases and so does the peak inser Tre pressure and the reverse is true for decrease in compliance while if there's only an increase in resistive uh airway pressure this is reflected only in the peak inspiratory pressure because it it's only from the change in the trans alol pressure here so there won't be any changes in the plateau pressure and likewise when resistance decreases um the other Peak pressure drops so just to recap and normally from from a normal system when we go to a high resistive Air High Resistance Peak inspiratory pressure increases while Plateau stays the same we see that in Airway obstructions and because flow pressure is also related to flow um high flow systems also results in increase in Peak and spiritual pressure in the bottom left graph here when the compliance is low both PE Peak and spure pressure and Plateau increase and this is seen in pulmonary edema ards fibrosis and hence forth so mean airway pressure reflects level of airway pressure during an entire um During the period of ventilation and it's reflected by the area under the pressured time curve and many many of the dilar effects of ventilation are um related to mean high mean Airway pressures now it can be m mathematically calculated because I said it's related to the area under the pressure time curve so mean airway pressure in a pressure Target of ventilation is the difference between the peak inspiratory and Peep multiplied by the ratio of inspiratory time to Total cycle time um plus Peep and because the shape of the pressure time scalar assumes the shape of a triangle in volume control ventilation this is factored by 0.5 now graphically um to give us an idea of what are the things that can increase meway pressure if the area under the curve of pressured time is are these blue boxes so we can see if we increase the flow depicted in box one that can increase the mean airway pressure we increase Peak pressure that will increase the overall area under the curve increasing mean airway pressure and lengthening inspiratory time and rate also has the same effect uh depicted in 3 and five um and in addition if there's increased peep that also increases the overall area under these curve so in summary pressure time scalar provides us with multiple information it helps us detect the mode of ventilation by looking at the graphics if it it gives us an understanding of the peak pressure Plateau pressures and mean pressure and identify um this the presence of Auto and in addition it also helps us understand the Dynamics of Airway obstructions and compliance flow time scalar is reveals a gradual change in inspiration and expiration flow over a period of time since Vol volume is a reflection of flow and time so it's the delivered title volume can be calculated by the area under the flow time scalar the inspiratory flow is predefined by the ventilator in most in all these instances so therefore the in inspiratory part of these scale Arts don't really help us provide don't really give us too much information about the compliance or the resistive properties of this respiratory system but since exhalation is or is passive and is not determined by the ventilator in most instances um we can we can understand properties of compliance and resistance from these so there are various forms of uh flows that can be set in a ventilator the commonly used flow patterns are the constant flow and the decelerating flow at either end of these graph having trouble moving these Mouse here so in constant flow pattern we can see Peak flow is reached immediately and is sustained through through the course of inspiratory cycle and then in sine wave flow this there's a gradual increase in inspiratory flow and then a gradual decrease and this resembles normal physiology in accelerating flow pattern the inspiratory flow gradually increases to a peak towards the end of inspiration and the revers and decelerating flow now um only volume targeted ventilation provides us an option of choosing from one form to the other but generally volume targeted ventilation uh employs constant flow pattern while pressure targeted ventilation employs decelerating flow pattern because in pressure targeted ventilation we must reach a predefined pressure immediately um and it should be and the pressure should be sustained so the decelerating flow pattern suits that model sine wave and accelerating flow waveforms are generally not found in most ventilators and um they are but they need to set it up that way so you need to ask a respiratory therapist because now in this ventilators I don't even know where they are they can still do them and from my understanding the thought behind using these sine waves and accelerating FL accelerating flow pattern was that it improved oxygenation because it provided an adequate amount of time for Alvi to be recruited but um there are no data to suggest that any one of these are better than the other um so in most cases constant flow is used in volume targeted ventilation and decelerating flow is used in pressure targeted ventilation so volume targeted scalar I'm sorry ventilators right all of our ventilators are going to be an autoflow right which is none of which is going to look decelerating but it's not truly decelerating it's going to change so it's a little bit different mhm so so in volume targeted ventilation sorry to interrupt you again but if you go back to the prior it is important because the older ones that were here probably Bruno can agree with me on this one we used to make modifications to this to the inspiratory flow wave forms particularly patient with ards or with COPD has he had a meaning I don't know if it truly gives you a meaning but that's another way that you change your time and another way that you actually change how fast this um uh breads are going in in the inspiratory time so it was typically thought or still we discuss that that you're going to use that square wave form when you're going to have an increment in your exhalation so patients who have obstructive disease compared to the accelerating wave form that you're going to use in patient who have restrictive lung disease you want to increase the inspiratory time in those patient so actually that dial that changes ITI has to do with the flow the FL pattern well don't think about it because you know it turns out to be a DI you agree Bruno with me I never disagree with you so in volume Target ventilation flow so in flow time KR flow is again on the y axis and times on the x-axis flow begins at Point a over here which is the beginning of inspiration and flow increases rapidly to point B to the defined maximum flow and remains constant at the same level through the inspiratory phase and when the defined title volume is achieved the flow drops immediately down to zero and thus the square pattern now if we are to do an inspiratory hole to assess the plateau pressure there will be no flow during between point e to point F and at the beginning of exhalation flow drop flow increase is again to point G which is the peak expiratory flow and then there's an exponential decline of um the exceleration wave to point from point G till the end till the beginning of the next cycle I'm sorry could you go back for slide one more so with the different the different kind of flow wave fors changing them you don't change your eye time your eye time is still the same you just change how you're delivering whether most of the flow is up front or later the consequence of changing your inspiratory time your flow has to change so if you're if you're changing your ID ratio meaning you know shortening your inspiratory time then you have to deliver the same amount of volume faster so you wind up usually with an accelerating um wave for yeah you ramp up your pressure to get that volume in much quicker than you would in a in a square wave they're much uh the the our current drers are it's a little bit harder to see it was much more readily apparent on our Servo vents because you can easily see as you made changes to your inspiratory time your scalers would all magically you know sort of correct themselves but that's what you'll see as Hector was alluding to when you change your it to e ratio you've got to deliver the the same volume faster so your pressure ramps up to do if that's the case then do any is there a particular flow that is more associated with body because if we were talking about it like earlier in your presentation you were talking about um the ideology of um pressure and the riseing pressure causing um injury to the lung so would there be one particular flow pattern that would be more likely to cause volum trauma yeah it's it's it's those types of flow patterns which is why most of our vents you you'll actually see in in the pressure regulated volume control mode you'll see you'll see that they they actually don't do that as a consequence because they'll what they'll gradually do is adjust the flow so that they can deliver the volume at a lower P so distension could be faster sorry but to answer your question I don't think that's completely known because the volume turns out to be the same you deliver the same amount is that rity so the that was one of the questions I remember that we used to discuss about ards how to manage one because if you deliver too fast you could increase the sheer stress not so much because of the amount Itself by rather than how fast you that particularly in the non sick areas of the usually goes there that's another rational why the cell wave form is preferred again that's what we used is it true Ian has been a trial I wouldn't be able to tell you maybe there is but that's the overall concept yeah CU I think it's hard out the the element of volume trauma versus the element of barel trauma it's very hard because one affects the other it just depends on which is the dependent and which is the independent variable so in pressure Target ventilation the decelerating flow pattern is used so here there is a rapid increase in the flow to achieve the peak flow and then to maintain the pressure there has to be a gradual drop and flow and eventually by the end of inspiration it drops down to zero and again if there's an inspiratory pause if there's an inspiratory pause yeah here it is so if there's an inspiratory pause there is no flow at this state and then the beginning of the exhalation starts over here with the deating flow pattern one thing I forgot to mention between all these three if we notice the decelerating flow pattern are all the same that's because they are patient defined and it's not ventilator driven so regardless of pressure targeted or volume targeted the bottom half of the flow time scalar looks very similar and um in pressure Target of ventilation it's this portion of the float of the scalar that actually can assist us with understanding patient compliance and resistance and um again compliance is the change in volume over change in pressure so we can assess P system compliance uh if the flow is zero at this point over here now um some some clinical applications of the flow scr during expiratory resistance which we see in Broncos spasms or COPD there would as I said there will not be any changes in the inser portion of the time of the flow scale art I'm sorry I'm just having trouble pulling up my mouse keeps running away here so um there's decrease in peak expert flow as expected with Broncos plasm and then there will be a curved Contour to the process of exhale ex of exhaling and then there's an increase time of the expiratory flow as well and following treatment with Bronco dilers or whatnot we can see an increase in the peak exploiture flow and then the expiratory time decreases and there's also less contouring when we have low compliance in the respiratory system this results in increased Peak expiratory flow because of the elastic recoil and then also the expiratory time is also shortened from because of the same effect and another phenomena that we're familiar and we look for in flow time scalar is the presence of Auto peep so in all of the preceding graphs graph s you notice that the expiration ended at the Baseline of zero flow now in the presence of Auto mouse keeps running away so in the presence of Auto peep we could see that there is air trapping thus you have that the expirat wave does not go back to the Baseline now um this can occur for multitude of reasons primarily if they're essentially what it's saying is you don't have adequate expiratory time to get back to the Baseline and we know the bad effectss of Auto in both uh the uh respiratory system as well as systemically so if you have a high respiratory rate or inadequate expiratory time you have Auto so which is depicted by the dotted line which is normal and then the solid lines the a patient that's Auto peeping uh too long of inspiratory time or prong the exhalation also results in Auto so the flow time scalar helps us on from the flow time scalar we can understand if it's a volume Target or pressure Target based on the inspiratory flow pattern and then we can detect Airway obstructions and compliance as well as the presence of Auto while volume time scalar shows gradual changes in the volume during inspiration and expiration so in Inspiration volumes uh there's a gradual increase in volume over the period of inspiration and once Target volume is achieved expiration in um occurs and the volume gradually drops back down to Baseline and when we play when we um do an inspiratory hold to assess Auto Peak this is reflected by flattening of the peak and the volume time scale the only difference between um a volume times KR scene in pressure control ventilation and volume control ventilation is there's a slight scooping that occurs because of the decrease in flow um because of the decelerating flow pattern so before I go on to the pressure volume and volume um flow volume Loops I thought I'll talk about compliance as pressure volume and flow volume Loops provide us a lot of information of compliance and that's one parameter that we assess so as I mentioned earlier compliance is the relative ease which is structure distends and two types of forces that we discussed earlier are the elastic and the resistive forces and compliance measurements are used to describe the elastic forces that oppose long inflation and compliance is the change in volume over change in pressure compliance is two comp components static and dynamic static compliance measurements are made during no Flow State that's when we employe an inspiratory hold so it's easy to understand from the pressure time scalar that static compliance is related to the plateau pressure I.E when there's no resistive forces involved um so static compliance describes primarily The Recoil of lung and thorax so static compliance is the change in volume which is a tital volume divided by the change in pressure in this case we use the plateau pressure to the Baseline pressure of P um and of course static compliance is increased in state is decreased with consolidation pemma ards and um external compressions well static compliances increased during empyema while Dynamic compliance is a combination of the resistive index as well as the compliance of the respiratory system and the reason being behind this is dynamic compliance talks about the compliance of the respiratory system there's air flow so that incorporates both the resistance as well as the elasticity of the respirator system and this makes and when we tie this back to the pressure time scalar it's easy to understand that this is related to Peak inspirator pressure so the dynamic compliance of the respirator system is the change in volume over the difference in inspirator pressures and the peak pressure so by assessing static properties of static compliance and dynamic compliance we can understand if there's a change in Airway resistance or if there is a combination of both very similar to how pressure time scalar uh we use pressure time scalar earlier so to illustrate one example if you have a decrease in the dynamic compliance and the static compliance is unchanged this would signify that the system the ponary system compliance uh is mostly increased because of Airway resistance and this should result in increase in Peak inp pressure and Plateau pressure and the other ones are self- exponent now Dynamic compliance curves are as I mentioned earlier you take flows volumes over small sample numbers through a flow and these are um excuse me and these are plotted with the use of um statistical models like the Le Square model and then you get a a damic um compliance curve the dynamic compliance curve is very similar to the inspiratory uh portion of a pressure volume Loop so for every change in pressure Dynam the compliance States what the change in volume would be so if there's an so the curve that we get is the slope um the slope reflects the compliance of the respiratory system if there's an increase in compliance the slope shifts to the left if there's decreased compliance the slope would shift to the right so to illustrate that the bottom curve a small change in pressure results in lesser change in volume compared to the top curves I'm sorry I can't pull my mouse otherwise it' be easier to demonstrate that but um so with this understanding i' like to talk about volume the pressure volume and flow volume loops and these Loops provide a dynamic Trend in of understanding the respirator system compliance and resistance so pressure volume Loop plots pressure on the x-axis and volume on the y- AIS it helps understand what the optimal uh alviola recruitment is and to measure patient compliance these Loops can either be static pressure volume Loops or dynamic pressure volume loops and static pressure volume Loops are essentially measured by stopping air flow for a period of time and measuring various points on the curve and plotting them while Dynamic pressure volume Loops uses steady flow and then using a mathematical model model you get the loops so a normal pressure volume Loop is elliptical in shape and it starts inspiration INSP it starts at Baseline zero and as inspiration occurs over change in Period of pressure the volume increases and this takes a in a mechanically ventilated patient this follows a counterclockwise turn and then once the ma deliver once the title volume that's desired is delivered expiration starts and the loop is completed and as you notice one thing the path of inhalation inspiration is different from from expiration so normally if we stretch a string it goes in the same path but in this case you see different Loops so for a pressure for instance of 20 the tital volume in the respirator system during inspiration is different to expiration and this process is called hysterisis and this is related to alv recruitment as well as uh surfactant and decruitment of alvioli in a non ventilated patient or a patient I'm sorry in a patient that's in breathing spontaneously on CPAP or um inspiration is usually patient driven so it's on the negative axis and it follows a clockwise turn so inspiration starts at 0 Z and goes upwards and overclockwise once delivered title volume is delivered expiration begins and follows a clockwise pattern now in patients that are that take their own breaths during mechanically ventilated during mechanical ventilation um patients own breath are depicted by this clockwise turn and then once a machine delivers a breath inspiration begins and it follows the clock counterclockwise turn and completes the expiration so the components of the pressure volume curve so the things that we can gather from a pressure volume curve are one at the Peak uh at the end of inspiration and start of expiration on the top right hand corner um we can determine what the delivered title volume is on the y- AIS and on the x-axis we could see what the peak inspirat pressure of the system is and if in the previous curve if you noticed the waveform started at zero but if there is a peep present or peep that was set and this is is reflected by um this the loop starts at that pressure of of peep that has been determined down here now at the peak of this curve at the maximum lenspure pressure and tital volume we could calculate the total Dynamic compliance of the system which is the change in volume to change in pressure the slope of this curve determines the normal compliance a normal compliance is about is set at 45° angle and even if the ventilator isn't set at this 45° angle we to orient yourself well we should alter the scale so that the compliance curve is set at 45° so that helps us understand what what process is going on now how does compliance change the pressure volume Loop so in volume Target of inhilation I mentioned that the the slope of this curve is at a 45° angle so if if we take a change in compliance whether it be increase or decrease this is affected by a change in the slope of this curve so during periods of increased compliance this curve overall curve would shift to the left which is the yellow curve and then if there's a compliance if compliance is decreased the curve would shift to the right over here now we notice that for the curve with decreased compliance to deliver the same title volume we require a higher level of peak ins per true pressure and Converse for this curves with less with increased compliance so decreased compliance more pressure to deliver the same amount of tile now in pressure targeted ventilation the pressure stays the same which is the preset pre uh Peak INSP pressure but in a system with less compliance lesser t volume is delivered because of the orientation of the curve here now what if it's just the airway resistance that changes how is that depicted on a pressure volume curve so the slope if it's a airway pressure that's increased resistance that increases the slope of the curve essentially stays the same what really changes is the inspiratory uh portion portion of the curve and another line to in parallel to this portion of the curve we see that there is a huge turn here and this is known as the inflection point so there are two inflection points in a pressure volume curve one is the lower inflection point of the inspir portion and then on the top here that's known as the upper inflection point the lower inflection point represents minimal pressure that's required to adequately recruit alvioli so so and then the upper inflection point represents a pressure that results in over distension of the Alvi now if we look at to illustrate this closer initially so as we see as this is the pressure volume curve as pressure increases there's a gradual change in volume but once adequate amount of Alvi rooted the change in volume becomes more dramatic and it's lesser to deliver smaller amount of tital volume with lesser pressure and then once we hit the upper inflection point the curve flattens so it becomes much more um more less more pressure delivers lesser amount of title volume at this point as well Junior can I stop you yeah so I like to use the analogy of blowing up a balloon so at the lower inflection point you know you you're really trying to get those alveoli open and once you do that's your low inflection point and once you get the Alvi up and distended as you distend and distend and distend and deliver more and more volume you hit your upper inflection point where again your compliance drops the more volume you try to deliver the stiffer the balloon gets that's that's sort of a an easy way that like to that's yeah those I'm getting on sorry um so as we can understand to keep the pressures between these two points of adequately H adequately recruiting the avoli and then not overstretching them if we keep the ventilation between these two areas this avoids large sharing forces and prevents volley trauma as well as barot trauma so there this there is a lot of thoughts on how this is done or this should be done but a large number of people advocate for setting the pee using the lower inflection point of a pressure volume curve and others also Advocate setting the peak inspiratory pressure at the upper inflection point of a pressure volume curve this is also how aprv Works in theory in theory and um there's also I didn't go into too much things about um C20 compliance but there's also another thought that setting inflation the 20 last 20% of the compliance curve if it's ratio to the dynamic compliance uh a ratio of one setting that would also help with avoiding Vol trauma but again these are all um different thoughts but clinically I don't know if they have how do you use it clinically how do you apply what you are saying do you know how to apply what you just set in a ventilator in front of a patient like ANS case yeah so let's say we have somebody in a volume control mode and we have um we we see that their Peak pressure is um 35 we want to ideally keep it below and we realize that the patient isn't doing well on it yeah sorry the plateau pressure um is TI so what we can do is if we are to use aprv in that instance we can choose the P High to be 30 and then the P to be set at P you complicate with or if we are to do inverse with the pressure controlled we will set the p p yeah um we can set the P peakin PR pressure not to exceed the plate pressure and then the P so that's what we all want that's an idea world right but every patient is different so you don't find the same so actually this is an exercise I have commented to some of the pH that I us used to have when I was a federal they asked me to do in every ards patient to actually determine what is the lower inflection point and the higher inflection point and the way you do it you keeps you are in front of the all the time you calculate your compliance start volumeid by PL pressure minus speed you keep changing those levels and you also see what your gases are what your oxygenation is like as well because that correlates with oxygenation as well so when you drop more than 20% of your compliance you are already rich your upper inflection point so you have to keep calculating your compliance at different levels of Fe because your Plateau pressure is very likely to enchange so you start with a set volume right you calculate your ards 6C per kilo whatever then you have your um uh Plateau pressure is set so the only thing that you're going to be modifying most would be your PE so that's exactly what Jeff is talking about what is your perfect P so then you calculate your compliance so you have to use the term that you just mentioned that volume divided by speed and then you see when you start dropping your compliance more than 20% you're already probably getting into your upper inflection point and very unlikely you are going to get more oxygenation benefit when everybody thought that oxygenation was the main point in ARS now we have questions about that of course but that's how the utility of that was um that's how I I mean took a long time but I never forget how this works after doing that so I invite fellows to do that often the other thing that this can be of help helpful as of help in a practical term it also indicates comfort in patients who don't have ards so if you have I don't know how many of you have seen the funny wave fronts in that particular way you can put it up all the time right there so you see that comes like this and does like this right in every inspiration do you see this this this and this how many of you have noticed that often does that that actually tells you that the patient is trying to pull pressures at different times so it indicat somewhat comfor the patient so when you start modifying your settings of f volume or whatever you need you may find the actual real curve that you want to see and so this is the other phenomena of beaking which we see when we go past the upper inflection point where you try to increase what Dr K has just finished saying now that if you try to increase the peak area pressure there's over distension with little change in tital volume and this is when problems occur so another things other things that we can infer from a pressure volume Loop is the work of breathing um it can again is thought of as work of breathing is the area under this pressure volume curve um over a period it's the integral of time of pressure and volume I should say so if we split a pressure volume curve so the pressure volume curve is this elliptical surface between a d c e a the elastic work is bound by the red triangle AB C while the resistive work of the inspiratory wing is bound by ADC a while AC which is the red tapos spere is the uh expirat portion of the resistive work that's done by a patient so if we are to grossly look at a curve and to see a system where there's increased compliance oops so where there's decreased compliance and there's normal resistance we see that the red part is tremendously increased so there suggest increased work of breathing because of compliance and then in the system where there's increased resistance um there is abnormal hysterisis so there is increased um this portion of the curve is increased so therefore work of breathing is more um because of uh increased resist of pressures so I'm going to try to run through this as I'm running out of time a flow volume Loop is basically plotted Flow versus time in volume control mode uh flow starts at time zero so in pulmonary function test flow is generally depicted inspiratory flow is always on the bottom half of the curve while exper is on the top in ventilators most ventilators um for some reason chose to use the inspiration on the top and the expiration at the bottom so and but there are also other ventilators which use the pulmonary function test way of labeling it so it's always just be careful to look at which way um a particular ventilator labels it which way the particular ventilator uh chooses to depict the inspiration expiration so inspiration starts at Time Zero where there zero flow um in aave wave for in a continuous wave uh flow pattern flow increases Peak at inspiration and then once this set title volume is achieved it drops down and during expiration a peak expiratory flow is reached and that's at the bottom left over there and then due to the passive process of expiration flow gradually um decreases and from these graphs we could see what the peak exper flow is uh deliver volume can be seen and the pattern of the loop could also be noticed now the this is also a flow volume Loop but if we notice this curve it looks like a mixture of of mirror reflection of this portion of the curve and that is because this is an a pressure control ventilation so here as we recall it in pressure control we use a decelerating flow pattern so flow reaches maximum intensity initially and then there's gradual drop in flow and that's why you have the shape that resembles the expert portion of a flow volume curve of in a in a um volume control ventilation so flow volume Loop can help us identify air leak so this is a this is a normal flow volume Loop there is the flow does not return back to zero this was suggest an air leak if you have increased Airway resistance there's decrease in peak expert Tre flow shown in the middle graph and there's that classic scooped out pattern um because of increased concavity and um following treatment you could see Improvement in these parameters Airway secretions is seen with these impedant in um air flow pattern and then in Auto peeps also noticeable in a flow volume Loop where flow does not return back to Baseline and over here so in summary when wave forms help providing us information on Airway mechanics and compliance with the respiratory system
Up Next
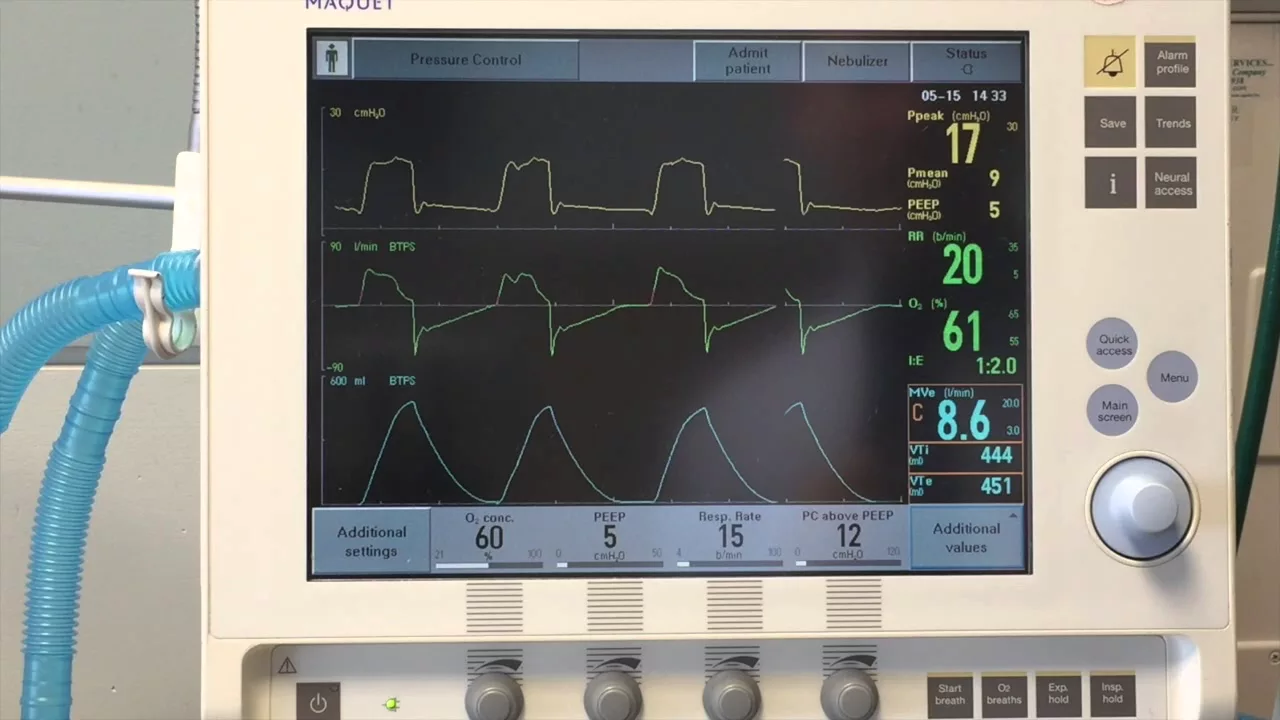
Mechanical Ventilation Basics for ICU House Officers
@rhsavel
842.8K views•2015-05-16

Rapid Quantitative Immunostaining of Intact Biological Systems
@simonscenterforthesocialbr1919
247 views•2015-12-02

Neuroanatomy: Central and Peripheral Nervous System Divisions Explained
@AKLECTURES
136.2K views•2014-09-20

Stages of Labor and Vaginal Birth | Childbirth Animation
@nucleusmedicalmedia
52.1M views•2017-08-18
Related Study Plans & Knowledge Roadmaps
Structured learning paths in Medicine