

























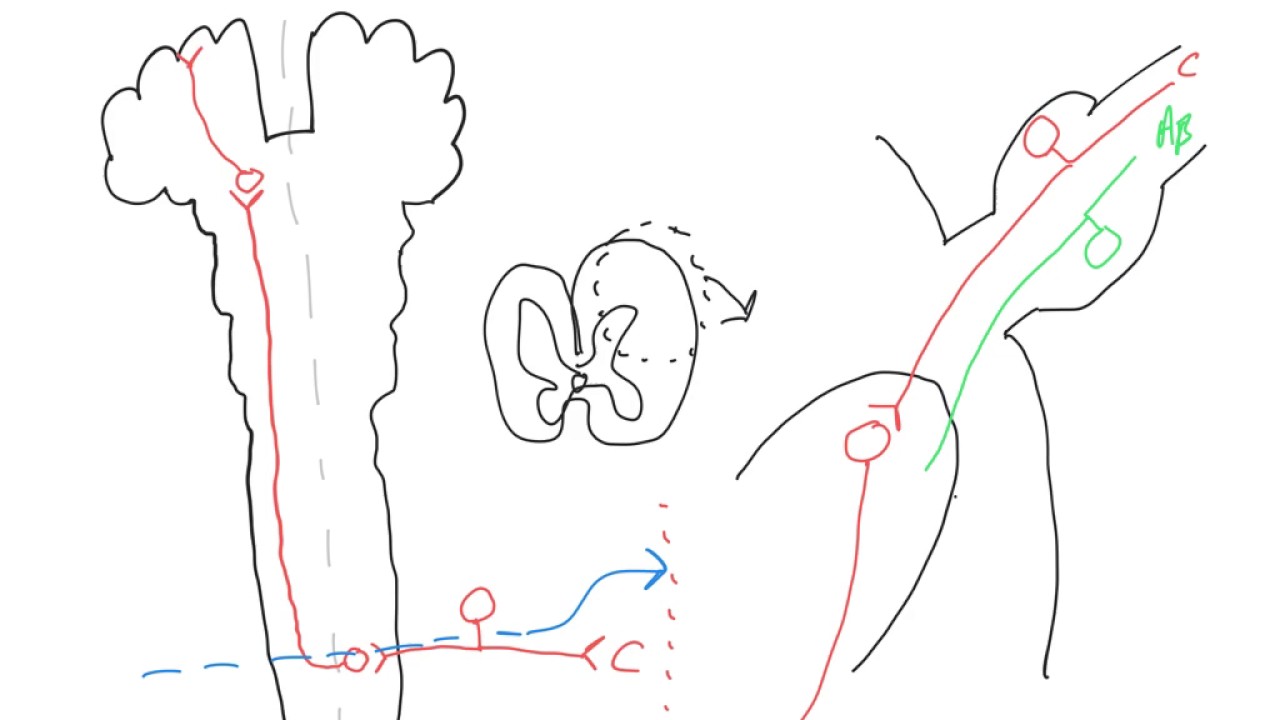

The Gate Control Theory of pain modulation, proposed by Melzack and Wall, explains how the nervous system regulates pain perception through two primary mechanisms: (1) spinal cord level modulation where large-diameter A-beta fibers (touch/pressure receptors) activate inhibitory interneurons in the substantia gelatinosa of the dorsal horn, releasing GABA and glycine to suppress pain signals from C and A-delta fibers; and (2) descending modulation from higher brain centers including the periaqueductal gray (PAG), rostral ventromedial medulla (RVM), locus coeruleus, and raphe nuclei, which release endogenous opioids (endorphins, enkephalins) and serotonin/norepinephrine to enhance inhibitory control over pain transmission. This dual system allows the body to naturally modulate pain intensity based on context and emotional state.
Pain Modulation: Gate Control Theory & Descending Analgesic System
Added:all right engineers in this video we're gonna talk about the modulation of pain it's equally as important as the pain pathway itself if you guys haven't already seen it please go watch the video on the spinothalamic tract where we talk about the anterior lateral system well dip into a little bit again in this video but we're not gonna do into super depth alright so pain modulation is super super important we're gonna talk about two different types of pain modulation and they're all endogenous and meaning that we all do it on our own inside of our body we make the chemicals that are necessary to be able to inhibit pain so what are these two analgesic systems so the two analgesic systems are the pain modulating systems is actually going to be regulate at two different levels so there's pain modulating modulation what are these two different pain modulations okay one that we're going to talk about first is the gate control theory and the next one we're gonna talk about is the descending analgesic system okay so we're gonna talk about these two now this gate control theory what's really really important all right let's take a scenario let's say I bumped my head against something sharp or something should hard and I hit it really hard and it hurts right it induces pain because of activating the a delts are activating the C fibers right and it says that information up to my cerebral cortex helps you become aware of it and where that pain is but there's a way that we can kind of lessen the pain if any of you I know that some of you guys have definitely done this if you hit your elbow against something or hit your head against something what do you do you rub it ah what why because it helps to kind of alleviate some of the pain how how does it do that okay we got to think what are we doing when we hit our head and then we start rubbing our head we're activating different types of touch receptors so in that situation here let's say that we do that we have the pain right so what's the painful stimulus let's say here here's the pain fibers and we're really gonna focus on it can be see and it can be a delta but we're mainly gonna be talking about this with respect to the C fibers but do remember the a delta R just is important in this - just the C fibers control more of this regulation okay so let's say that there was pain right so there was some type of painful stimulus or some type of extreme temperature stimulus and these were activating these fibers right and from that it was activating me peripheral processes then the central processes and we said that the C fibers particularly they go to a specific part in the spinal cord remember the Rex lamina we divided them into different like partitions there was a specific one right here it was called lamina - okay and lamina - has a special nucleus right here a special nucleus and right here is this nucleus this guy is important because in lamina - the rex lamina - there's this special structure here which is called the substantia gelatin oza of Rolando and then from here we'll activate some more axons and then cross over here and move up right through the anterior lateral system so we know that there's a pain and temperature pathway mainly regulated by the C fibers that we're going to talk about going to lamina - that's important and again what is that lamina - a trex t' lamina - is going to be called they call this the substantia gelatin oza of rolando holy crap right so there's a lot of that one and there's another one that I can't sign apps on this is the main one there's also the nucleus propria switch is in Rex land on a three button main one here substantial gelatin nose of Rolando so now we know this pain pathway now something I didn't discuss in the pain pathway the actual video we talked about the spinothalamic tract and I'm just gonna mention it really quickly here let's say here I have C fibers which are represented here in red so here's my C fibers and then over here which I want to do in this baby blue is going to be my a delta fibers okay they come into the spinal cord right we know that these guys come into the spinal cord and they sign apps on some second-order neuron and then crossover same thing over here with the actual C fibers they come to some second-order neuron and crossover well the question is that we have to be able to ask ourselves is what chemical is actually being released in this synapse cuz that's important because it actually determines a little bit of why fast pain is fast and why slow pain is slow so these C fibers are regulating slow pain and they believe that the chemical that is released at the synapse point is a chemical called substance P okay substance P is important in the synapse to stimulate these second-order neurons to go and actually send up through the ascends through the anterior lateral system but what about the chemicals with the a delta fibers what chemicals are they releasing to actually stimulate this second-order neuron and then send the action potentials upwards because again they're going up and going up here's the anterolateral system this chemical that they're releasing into that synapse is called glutamate and this one causes excitation a lot faster and a lot heavier this substance P is a little bit of a slower activation substance P you know what else is it's important for it's also important because you can release substance P wherever there's stimulus remember the stimulus for this was pain and temperature these were the stimuli here what's important here is that the chemical factors that are actually a cause that actually released like they're from histamine and protons and potassium and all that stuff what's really important is that substance P can actually be released down here too and what it does is substance P through what's called an axon reflex it can be released out there where all these chemical mediators are and what it can do is it can actually decrease the threshold for pain okay so we can decrease the threshold needed to activate the noisy acceptors and transmit the pain that's really cool okay so now that we understand that these are the chemicals that are released through those synapses for the slow pain pathway at substance P for the fast Bane pathway its glutamate let's come back over here for a second we said if we hit our head we're gonna send this action potential upwards now I start rubbing my head out hurt what am I going to activate I'm gonna activate a bunch of different touch receptors let's do these in orange so here is going to be some touch receptors let's say that it's going to be some type of touch receptor or coming from a pressure receptor whatever right something like this these get activated by me rubbing my head and touching that right when it does that it sends these action potentials into where the poster Gary horn they go into the posterior horn and where do these fibers usually go for the pacinian corpuscles the meissner's corpuscles all those guys if you know they go into the dorsal column and ascend upwards as the fasciculus chrysella circuitous but something's really cool they give off little collaterals they give off little collaterals that can come over and actually stimulate a little inhibitory neuron and we're gonna zoom in on that and see how that actually works so we're gonna come over to this cross-section of Bionicle but I want you to remember that whenever we hit our head we have a painful stimulus a way that our body can control that pain at the gate the spinal cord is by rubbing that area and by rubbing that area caressing the area it can cause those fibers that are going into the dorsal contract to give off collaterals let's look at that so let's say here was our pain fiber all right it's bringing information into substantial gel tones of Rolando and then from here this guy is going to cross over right we know it'll go through the anterior commissure then we said over here was going to be for the touch for pressure maybe even a little bit of stretch receptors or vibration receptor stuff like that they're gonna come in and they're going to go into the dorsal column and ascend upwards right they're going to go up eventually up to the medulla where they'll become a part of the medial meniscus eventually but what happens is we said that these give off collaterals they give up these collaterals there's these little inter neurons there's these little inter neurons right here and this Rex lamina right in again what was this Rex lamina right here if we said it was Rex lamina to where the substantiate gelatin oza over Lata is if you have a lot of stimulation due to the touch okay a lot of touch stimulating these fibers what are they going to do some of the action potential is going to spill over into this collateral when it spills over into this collateral it's going to stimulate this little inhibitory neuron when it stimulates that inhibitory neuron guess what happens that inhibitory neuron starts releasing certain types of chemicals what type of chemicals you ask mainly gaba okay so they start releasing chemicals into the synapse called gamma amino butyric acid and what that does is is that inhibits it can inhibit two points it can either inhibit the actual the substantia gelatin oza where the nucleus is the actual cell body is or it can inhibit the actual synaptic terminal so this actual synaptic bulb here of this incoming neuron that's the central process from the dorsal root ganglion right either way if you inhibit that can the action potentials that are being sent from his pain pathway these pain fibers this is from pain and temperature right these are being sent down this if you inhibit this pathway what's going to happen to the pain pathway the pain information that's going over and up you're going to decrease the action potentials if you decrease the action potentials what's that gonna do for the actual paint it's going to decrease the actual severity of the pain so this is going to try to decrease pain perception I think that's so cool alright and this should make sense it should make sense okay so again with this part remember that this part here was for the dorsal column medial meniscal pathway and it gives off little fibers collaterals that stimulate these in little inhibitory interneurons which can send released certain types of inhibitory chemicals like gaba to inhibit these neurons from sending action potentials through the anterolateral system modulating the pain so that's called our gate control theory alright sweet deal so we have that and again recap it who is controlling this dorsal column medial meniscal pathway this was important because of their collaterals so now we have to talk about this descending analgesic system there's so many different structures here that are controlling this actual are modulating the pain at the spinal cord level a couple of them that we're gonna talk about here is the perry a quid ductile grey matter we're gonna talk about this when we diet when we illustrate them in the diagram we refer to as PA G period echo dr. gray matter another one is the peri ventricular gray matter probably mark they says P V G periventricular gray matter and then there's another one here which is going to be called the locus coeruleus and some other ones here like the reticular formation and we'll talk about another one which is going to be the raphae nucleus Magnus all these are really really important gray matter structures that I can control these descending fibers so let's go ahead and talk about those alright so a little bit of neuroanatomy here's our thala my alright so here's the thalamus now in between the thalamus is actually going to be this little cavity and this little cavity here is called the third ventricle so this is our third ventricle there's pieces of gray matter right around it so what do you think is called peri ventricular gray matter fun simple so these are really important so you have the peri ventricular gray matter they're gonna send these descending fibers down now another thing what does this structure right here well this structure here is running through the midbrain and it's the continuation of the third ventricle alright it connects it to the inferior you there's the fourth ventricle this structure right here is called the cerebral aqueduct this blue structure here well there's actually some nuclei that are surrounding this cerebral aqueduct so what do you think they're called they're called the periaqueductal gray matter and that's these little red guys here alright so you have the periaqueductal gray matter and the periventricular green matter what these guys do is they can send some fibers down but they actually come over here and they can activate a whole bunch of other different types of nuclei what are some of these other nuclei let's say over here in the midbrain in the midbrain you have these other structures here and this is going to be these guys are really really rich and epinephrine they're rich in norepinephrine and because they're rich in norepinephrine these guys here this is where we find what's called the locus coeruleus all right now the locus coeruleus is gonna get stimulated by the periventricular grey matter the pair you collect a grey matter right so again what were their structure here this was a periventricular grey matter and that's when I here's the periaqueductal grey matter they might be able to stimulate this locus coeruleus right what else you know there's other stimulations that they can give to right here they have the reticular formation the reticular formation also has some special nuclei that are located there and these guys got a heck of a name this one right here but actually the nuclei in this area is called the para giganto celulares reticular nuclei okay so you have the pair of giganto cellular is particular nuclei located within the reticular formation these are important and again why because these guys are actually going to be rich in another type of neurotransmitter which is called serotonin okay so they're rich in what's called serotonin also called you can call it 5-hydroxytryptamine now there's one more area which is also important the perio doctor grey matter can also give stimulation to these nuclei these green nuclei are actually called the raphe nucleus magnus so what would you call these ones the Roth a nucleus magnus these are some funky names right but these are also going to be rich in serotonin okay so you have the locus coeruleus which is rich in norepinephrine and you have the raphe nucleus magnus and the pair giganto sailors say layers reticular nuclei they're rich in the serotonin neurons now either way let's bring these guys together okay and let's bring all of these guys together down here because they're gonna descend right to this area here okay now when they descend they actually go through a part like the posterior lateral aspect over here in the lateral white column and then they come down and they synapse on those cell bodies where the substantia gelatin oza of rolando is so again all these fibers can come down and sign apps right down there and they can release what type of chemicals accordingly if we're talking about the locus coeruleus this is going to be Noro epinephrine releasing neurons and if we're talking about the pair giganto solaris and the raphe nucleus Magnus these are releasing what's called 5-hydroxytryptamine also known as Cerro tonin now what happens here they go down here and they secrete that serotonin in that five hug us serotonin and norepinephrine onto little inhibitory neurons so how let's come over here and see so since we've occupied a little bit of this area let's occupy this other area now okay so now we're going to come over here and let's pretend for a second that now we're going to have that pain fibers are going to be coming in over here now so let's say here is going to be the pain fibers coming in from this side right activate it through some type of painful stimulus comes in synapse is here on the cell bodies of the substantial gelatin nodes of rolando cross over and then a ascends right through the anterior lateral system or the spinothalamic tract now over those guys here we have the pair giganto celulares from the actual reticular formation we're gonna have the Roffe a nucleus Magnus and we're gonna have the locus coeruleus fibers coming down here and releasing what type of chemicals they're gonna be releasing norepinephrine and 5-hydroxytryptamine you know what they release it on there's little inhibitory neurons little inhibitory neurons here let's say it's right here this little inhibitory neuron is going to be stimulated by the norepinephrine and by the 5-hydroxytryptamine and guess what it's going to do it's gonna come over here and it's gonna see create special chemicals very very special chemicals these chemicals that is going to be secreting is going to inhibit the substantia gelatin owes over Londo from sending action potentials down and if there's less action potentials being sent up through this system then what's going to happen to the pain perception it's gonna decrease now what are these chemicals that it's releasing and the reason I'm telling you why it's why we need to know these chemicals is because you know there's chemical that we give usually to people to help to alleviate pain like morphine well these chemicals that are being released here are very very similar to morphine what are some of these chemicals that they're releasing there are releasing what's called in Kathleen's endorphins and another one called Dyne orphans all these chemicals are basically like natural opioids basically things are basically our endogenous meaning that you make them inside your own body opioids okay these are endogenous opioids so you have a way to be able to reduce pain okay now the question is that you guys should have is we know how to modulate pain but how do these nuclei know when to fire that's important to ask yourself how do these nuclei know when to fire these action potentials downward to inhibit these actual neurons that are sending action potentials upward it's the ones that are going up so remember if we have the fibers coming up here pretend we have the anterior lateral system coming up right here so here's your anterior lateral system ALS right some of these fibers you know this what's called the spine Omi's and cephalic fibers the spine oh Mazen cephalic fibers they were coming off of that anterolateral system or the spinothalamic tract they can stimulate the periaqueductal gray matter so lots of action potentials coming up - this means that there's a lot of pain so that means that you should stimulate this guy to give descending pathways to help to modulate that pain and then this should make sense what else upper higher brain structures what kind of structures so some of the structures that can influence these guys - periventricular and the periaqueductal what are some of them some of them is going to be the actual limbic nuclei so some of the limbic nuclei for example if you're with a cingulate gyrus the insular cortex the hypothalamus there's so many different structures that can come down here and regulate the periaqueductal gray matter what else parts of the cerebral cortex maybe even the sensory cortex the sensory cortex can send down information here so even the sensory cortex has the ability to let the periaqueductal gray matter know sensory cortex okay and then let this peri o'clock the gray matter know when to fire action potentials downwards and these Perrigo dr. gray matter and periventricular gray matter they also can release in Cathal ins alright so different types of endogenous opioids so what are three ways that you could actually stimulate this descending pathway one is through this anterolateral system where the spinal attractive is coming off words you can give off fibers what type of fibers spino means in cephalic fibers what else sensory cortex can also tell the gray matter okay just fire some information down other limbic nuclei like the hypothalamus or the anterior in some insular cortex or the cingulate gyrus they can tell it also so it's a beautiful beautiful system hi guys so that pretty much covers everything that we need to know about pain modulation I really hope it made sense I truly do if you guys did please hit the like button comment down the comments section and please subscribe guys also check out our Facebook or Instagram and maybe even our patreon account if you guys have the opportunity to donate we'd really appreciate it our engineers as always until next time [Music] you [Music]
Up Next

Glial Cells Microglia & Astrocytes in Brain Inflammation
@KaplanCenter
7.6K views•2017-07-06

Investigating Circuits of Conditioned Fear | Greg Quirk
@MichiganEngineering
1.9K views•2016-06-20
Motor Neuron Lesions: UMN vs LMN - Neurology Guide
@NinjaNerdOfficial
880.5K views•2020-11-01

How Exercise Benefits Your Brain: Science Explained
@TED
11.4M views•2018-03-21
Related Study Plans & Knowledge Roadmaps
Structured learning paths in Neuroscience