































The anion gap, calculated as sodium minus the sum of chloride and bicarbonate, helps classify metabolic acidosis into two categories: normal gap (hyperchloremic) acidosis, where bicarbonate decreases and chloride increases in a one-to-one ratio without producing new unmeasured anions, and elevated gap acidosis, where excess production of pathologic acids creates unmeasured anions that lower bicarbonate without increasing chloride; hypoalbuminemia must be corrected using the formula adjusted anion gap = measured anion gap + 2.5 × (4 - albumin [g/dL]) to avoid missing mild acid-base disturbances.
Anion Gap in ABG Interpretation: Calculating & Classifying Metabolic Acidosis
Added:Basic principles of acid-base physiology, including the definition of pH and the bicarbonate-carbonic acid buffering system.
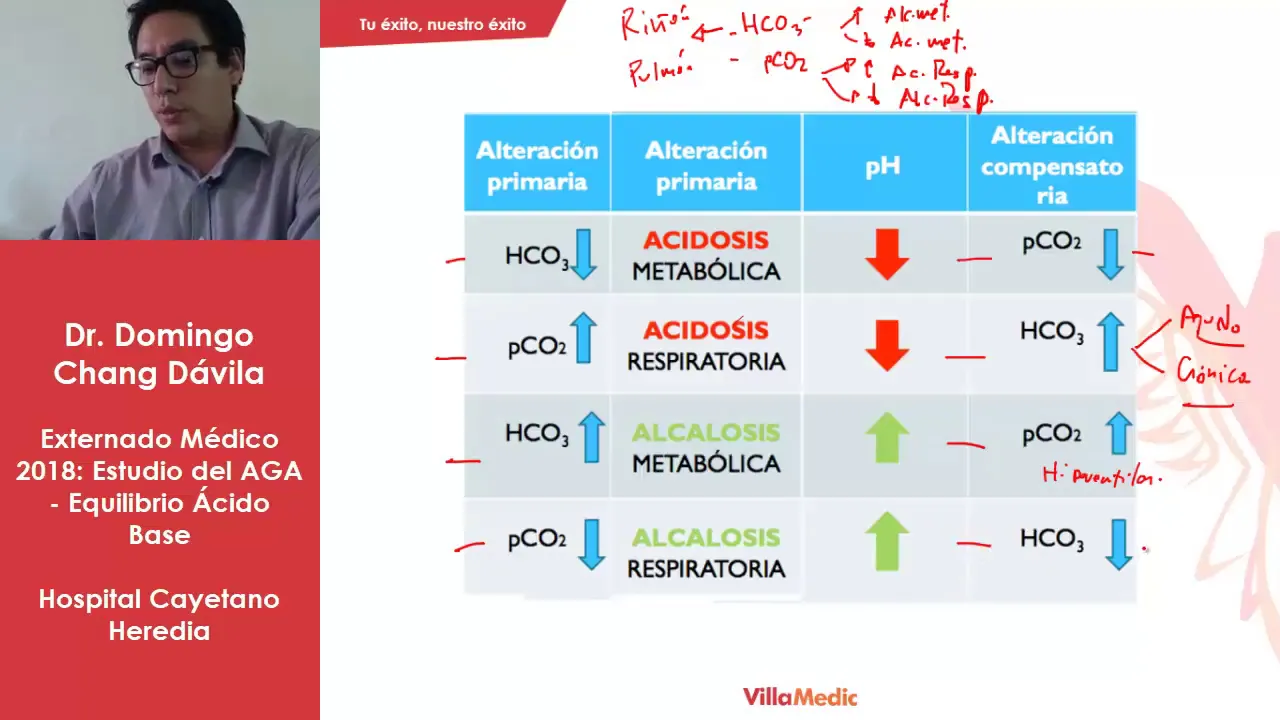
How to interpret standard Arterial Blood Gas (ABG) values to identify primary metabolic acidosis.
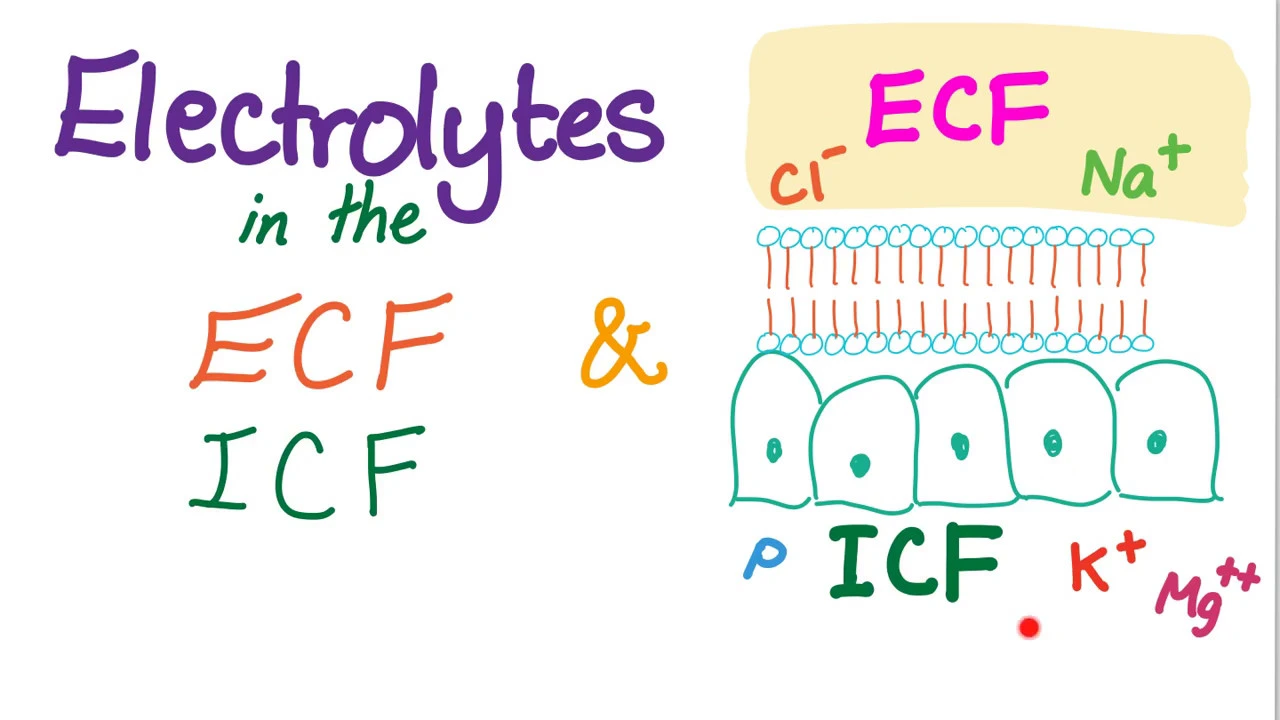
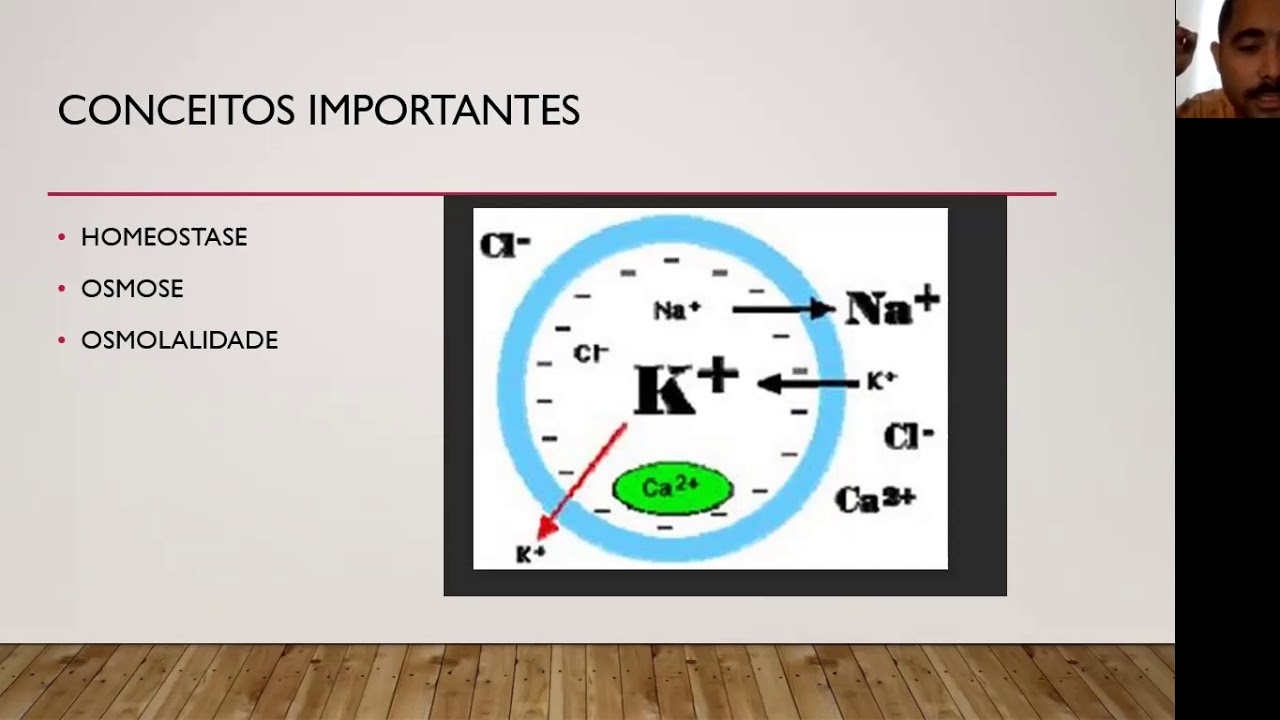
The biochemical principle of electroneutrality in bodily fluids (the balance of cations and anions).
Normal reference ranges and physiological roles of major serum electrolytes, specifically Sodium (Na+), Chloride (Cl-), and Bicarbonate (HCO3-).
Differentiating the etiologies of High Anion Gap Metabolic Acidosis (HAGMA) using clinical frameworks like GOLD MARK or MUDPILES.
Investigating the causes of Normal Anion Gap Metabolic Acidosis (NAGMA), focusing on Renal Tubular Acidosis (RTA) and gastrointestinal bicarbonate loss.
Calculating and interpreting the Delta-Delta (Delta Ratio) to identify complex, mixed acid-base disorders.
Applying corrections to the calculated anion gap in patients with hypoalbuminemia to prevent underdiagnosing HAGMA.
Formulating clinical management plans for specific causes of metabolic acidosis, such as diabetic ketoacidosis (DKA) or toxic alcohol ingestions.
209.3K views1.9Klikes18:57Original Release: 2012-02-11
hello this is the fifth lecture of this course on interpreting ABG's and i'm eric strong from the Palo Alto Veterans Hospital and Stanford University today I will be discussing the anion gap and how it is used to classify different types of metabolic acidosis the learning objectives are as follows first to understand the origin of the anion gap next to be able to list the major factors that affect the anion gap including how to correct the anion gap for hypoalbuminemia finally to be able to distinguish an elevated n ion gap metabolic acidosis from a normal ni gap metabolic acidosis measurement of the anion gap is a critical step in approaching the differential diagnosis of a metabolic acidosis an elevated anion gap indicates the presence of a non routinely measured anion which is usually caused by the production of a pathologic acid let's take a closer look at exactly what the anion gap is in the body the concentration of cations needs to equal the concentration of anions in order for us to be electrically neutral more exactly the concentration of positive charge needs to equal the concentration of negative charge in the serum the vast majority of positive charge is carried by the sodium ions a concentration of 140 millicoulombs per liter is typical potassium ions have a small but easily measured concentration usually about 4 then there are a number of cations which are less frequently or less easily measured these include calcium magnesium and various positively charged proteins negative charge in the serum is largely carried by chloride and bicarbonate here are some typical values for those ions in addition there are ions that are less for only or less easily measured they include phosphates sulfates and negatively charged proteins as you can see the amount of unmeasured anions just happens to exceed the amount of unmeasured cations this difference between the two is the anion gap as you can see from the diagram potassium is usually lumped together with the unmeasured cations despite it always being measured concurrently with sodium I suspect this is because the absolute value of I which potassium can vary between patients is so small that it has negligible impact in the anion gap assessment mathematically we can say that the ni gap is equal to the unmeasured anions - the unmeasured cations including potassium this is equivalent to sodium - the sum of chloride and bicarbonate the normal range for the anion gap is approximately 812 mil equivalents per liter but is lab specific and you should really check with your own lab for its normal range before drawing conclusions about a patient's acid-base status for purposes of the remaining lectures of this course I will assume that the upper limit of normal is 12 an uncommon alternative to the above calculation is to include potassium thus the anion gap is equal to the sum of the sodium and potassium minus the sum of the chloride and bicarb using this alternative one would expect the normal range to be closer to 12 to 16 let's see a graphical representation of the electrolyte differences in normal gap and elevated gap metabolic acidosis first here is our normal acid-base status with some normal values of commonly measured cations and anions this demonstrates a normal anion gap of 12 which is 140 - 24 - 104 in a normal gap metabolic acidosis bicarbonate concentration is decreased and chloride is increased in roughly a one-to-one ratio this can be seen with either loss of bicarbonate or decreased excretion of acid by the kidneys as you can see there is no change in the value of the sodium minus bicarb - collide thus the anion gap is unchanged due to the fact that that chloride is increased a commonly used synonym for a normal gap metabolic acidosis is hyperchloremia metabolic acidosis in an elevated gap metabolic acidosis there is usually excess production of a pathologic acid which becomes an unmeasured an eye on when it dissociates and is buffered by bicarbonate the bicarb is thus lowered but chloride is not increased in response so the anion gap is elevated the only cause of an elevated gap acidosis not caused by excessive production of a pathologic acid is severe renal failure in which the kidneys are no longer able to normally excrete phosphate and sulfate leading to their accumulation in the blood and which contribute to the concentration of unmeasured anions I will discuss the differential diagnosis of both normal gap and elevated gap metabolic acidosis in more detail and later lectures however I'll quickly run through the list to give you an idea of how assessment of the anion gap can assist with determining possible diagnosis a normal gap metabolic acidosis can be due to either the loss of bicarbonate or due to decreased renal hydrogen excretion the former can be due to diarrhea or various forms of GI drainage type 2 renal tubular acidosis the carbonic anhydrase inhibitor acetazolamide and as a chronic complication of your readable diversion surgery decreased renal excretion of hydrogen can be seen in renal failure or either in type 1 or type 4 RTA the latter being largely synonymous with hypoalle doctrine ism ideologies of an elevated gap acidosis are a bit more complex you may recall this diagram from lecture 2 I will save a detailed discussion of this for later but very briefly on the left Rav of pathologic processes and on the right are the unmeasured anions that accumulate and lead to the elevation of the anion gap here is the same information displayed slightly differently first lactic acidosis as a consequence of numerous different processes can lead to accumulation of lactate ketoacidosis from DKA alcohol ingestion or starvation leads to accumulation of acetoacetate and beta-hydroxybutyrate which are collectively known as keto acids though this is a bit of a misnomer as the latter is not actually a ketone methanol ingestion leads to formic acid and ethylene glycol is metabolized into glycolic like oxalic and oxalic acids Halloween inhalation from sniffing glue if evaluated very soon after the exposure can lead to high levels of hippie uric acid finally the acidosis which usually accompanies renal failure is the only example of one which can have an elevated anion gap but without the production of a new pathologic acid rather as just mentioned in renal failure a deficiency and excretion of phosphates and sulfates occurs which contributes to the amount of unmeasured anions there are a number of pathologic states that can result in alterations in the anion gap that are completely unrelated to a metabolic acidosis a high anion gap can be caused by metabolic alkalosis by a subtle secondary increase in albumin concentration as well as an increase in the negative charge of each albumin molecule in the presence of higher ph phosphate is an unmeasured anion which is not accounted for in the calculation of anion gap thus severe hyper phosphate emia may cause a mild anion gap increase lastly an anionic para protein emia could also do this though this is rare as most power proteins are either electrically neutral or positive charge a low anion gap is predominantly caused by low albumin since albumin is one of the primary unmeasured other causes could theoretically include excessive concentrations of any cation including potassium calcium magnesium and even lithium bromide zom can lead to a falsely low anion gap as some lab equipment registers bromide as chloride this can be seen with therapeutic levels of peridot stigman bromide sold under the brand name of Mastodon and used for myasthenia gravis finally the presence of a cationic power protein such as a monoclonal AGG in multiple myeloma can also lead to a low anion gap in fact an unusually low anion gap in the absence of an obvious electrolyte disturbance or hypoalbuminemia may prompt an evaluation for multiple myeloma as hypoalbuminemia is the most common cause of a low anion gap a formula has been empirically developed in an attempt to adjust the anion gap to account for it the equation for this is as follows the adjusted anion gap in metal equivalents per liter equals the measured anion gap plus 2.5 times 4 minus the albumin as measured in grams per deciliter the reason to adjust for hypoalbuminemia is to prevent missing mild anion gaps for example a patient found to have an anion gap of 14 might not initially alarm a treating physicians however if that patient was found to have an albumin of 1.5 the expected anion gap would no longer be 12 mil equipments per liter but rather 6 less instead of the patient's anion gap of 14 being 2 higher than the upper limit of normal and is actually 8 higher than what would be expected which would be more concerning another way to look for this issue would be to use this equation so for example if the measured anion gap is 14 you would add 2 point 5 times 4 minus 1.5 this is approximately 20 which would more than likely trigger additional investigation the adjusted anion gap essentially tells us what the anion gap would be if the patient had a normal album in order to see how analysis of the anion gap works in practice I'm going to go through four quick examples before that however I just want to quickly go over this notation which is commonly employed on the wards in the United States but with which you may not be familiar if just starting out or if practicing elsewhere in the world essentially you take this specific pattern of lines and around it write the values of the basic metabolic panel this is the arrangement of values that has become standard Convention and I will use this notation frequently throughout the remaining lectures I will also follow us convention regarding units so sodium potassium chloride and bicarbonate will all be in milla equivalents per liter while the urea which we inexplicably call the B UN creatinine and glucose will all be in milligrams per deciliter so here is example number one we have a pH of 7.3 to AP co2 of 28 and a bicarb of 14 step number one as always is to look at the pH here we immediately see this patient has in acidemia step number two is the check the of the pco2 since DP co2 is deranged in the same direction as the bicarb the process is metabolic and thus a metabolic acidosis from the last lecture you know that step number three is to evaluate compensation for a metabolic acidosis we use winters formula which asks whether the measured pco2 is approximately equal to one point five times the bicarb plus eight one point five times 14 is twenty one plus eight is 29 so yes the equation holds true we conclude that we have appropriate compensation from this lecture we will now add in step number four which is to calculate the anion gap the anion gap equals sodium minus the sum of chloride and bicarb plugging in our numbers of 140 116 and 14 we calculate the anion gap to be 10 mil per liter as we are not given an albumin we will need to assume it is normal and thus the anion gap does not need to be further adjusted so we haven't appropriately compensated metabolic acidosis with a normal anion gap or stated more succinctly a normal gap metabolic acidosis example number two pH 7.28 pco2 24 bicarb 12 step one the low pH tells us that this patient has an acid emia as step two the concurrent Lelo pco2 tells us that it is a metabolic process and therefore a metabolic acidosis for evaluating compensation we use winters formula again does the pco2 of 24 approximately equal 1.5 times 12 plus 8 and it's close enough to call good thus compensation is appropriate our anion gap again is sodium minus the sum of chloride and bicarb so 128 minus the sum of 94 and 12 which is 22 thus this patient has an elevated gap metabolic acidosis for example number three let's try something a bit more complicated this time we have a very brief clinical vignette the patient is a 58 year old man with diabetes and chronic kidney disease who presents with an abrupt onset of dyspnea two hours ago his pH is 7.47 with AP co2 of 20 and a bicarb of 14 the elevated pH tells us the patient is alkaline m'q since the pco2 is arranged in the opposite direction as the ph the process must be respiratory in origin so this patient has a respiratory alkalosis next evaluate compensation the vignette strongly implies that the process is acute therefore from our last lecture on compensation we know that an acute respiratory alkalosis the bicarb should be increased by two metal equivalents per liter for every ten millimeters of mercury the pco2 is below 40 with a pco2 of 20 we would expect the measure bicarb to be 20 since it isn't compensation isn't appropriate and another disorder is present as 14 is significantly lower than 20 and thus trending more towards acidemia it implies the additional process is a metabolic acidosis it's important to note that this metabolic acidosis just identified is not just compensation for the respiratory alkalosis that we first identified but rather an independent primary acid-base disorder for step number four let's calculate the anion gap 135 minus the sum of 114 and 14 is 7 in summary then this patient has a respiratory alkalosis and a normal gap metabolic acidosis here is our last example a 48 year old woman is found unconscious next to an empty pill bottle at home her pH is seven point zero nine P Co 234 bicarb ten step one we have an acid emia step two the low pco2 tells us that she has a metabolic acidosis step three for compensation we once again use winters formula and ask if the pco2 of 34 is approximately equal to one point five times the bicarb of ten plus eight it does not therefore compensation is not appropriate as the pco2 is higher than expected and trending more towards in acidemia the additional acid-base disorder is a respiratory acidosis the anion gap in this case is 12 mil equivalents per liter which at first looks normal but let's not forget that now we are given an albumin and that's not normal normal albumin is approximately 4 grams per deciliter so we must adjust the anion gap for the hypoalbuminemia the anion gap adjusted equals the anion gap measured plus 2.5 times the difference between 4 and the measured albumin for this patient this will be 12 plus 2.5 times 4 minus 2 therefore the adjusted anion gap is 17 and our final diagnosis is an elevated gap metabolic acidosis and a separate primary respiratory acidosis so that's the ni gap and it's basic role in diagnosing acid based disorders in the next lecture I will discuss the anion gap a little further and specifically how it can be used to diagnose triple acid based disorders you
Up Next

7:29
Assessing Metabolic Compensation: Simple Rules for Acid-Base
@MedMastery
109.9K views•2018-03-21

37:45
Rapid Quantitative Immunostaining of Intact Biological Systems
@simonscenterforthesocialbr1919
247 views•2015-12-02

9:38
DLCO Explained: Diffusing Capacity in Pulmonary Function Tests
@StrongMed
267.6K views•2014-03-06

3:05
Stages of Labor and Vaginal Birth | Childbirth Animation
@nucleusmedicalmedia
52.1M views•2017-08-18
Related Study Plans & Knowledge Roadmaps
Structured learning paths in Medicine
medicine
Interpreting PFTs: Spirometry & DLCO
01Respiratory Anatomy and Physiology Foundations
02Spirometry: FVC, FEV1, and Flow-Volume Loops
03Lung Volumes and Plethysmography
+ 2 more learning modules
12h5 modules
Explore Roadmap
medicine
Abnormal LFTs: Diagnostic Workup & Pathology
01Liver Anatomy and Basic Physiology
02Introduction to Liver Function Tests (LFTs)
03Hepatocellular vs. Cholestatic Patterns
+ 3 more learning modules
12h6 modules
Explore Roadmap
medicine
Analyzing Blood Smears: RBC, WBC & Platelets
01Introduction to Blood Components & Smear Preparation
02Normal Morphology of Blood Cells
03Erythrocyte Pathologies & Morphological Variants
+ 2 more learning modules
12h5 modules
Explore Roadmap
medicine
Mechanical Ventilation: Waveforms & Alarms
01Anatomy and Physiology of Breathing
02Introduction to Mechanical Ventilation & Core Modes
03Ventilator Settings and Waveform Interpretation
+ 2 more learning modules
12h5 modules
Explore Roadmap